Patient Presentation
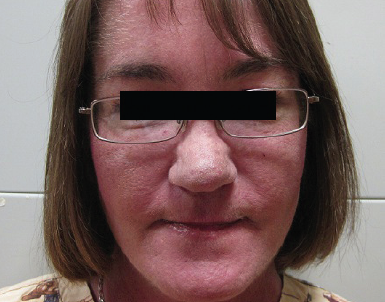
A 46-year-old female presented with painful blisters on her dorsal hands. She reported two previous similar episodes but denied other medical problems aside from perimenopausal symptoms treated with estrogen hormone therapy. On physical examination, the patient had erythematous, flaccid bullae localized to the dorsal hands, bilaterally (see Figure 1). She also had fine hypertrichosis of her temples and preauricular cheeks. She had subtle sclerodermoid changes including perioral rhytids and she appeared older than age stated (see Figures 2 and 3).


 Figures 1-3, left to right
Click on the image to see a larger version.
Figure 1. Bilateral flaccid bullae of dorsal hands.
Figure 2. Preauricular hypertrichosis.
Figure 3. Subtle perioral rhytids.
Two 4-millimeter punch biopsies were obtained and submitted for hematoxylin and eosin stain (H&E) and direct immunofluorescence (DIF) in addition to bacterial and viral cultures.
WHAT IS YOUR DIAGNOSIS?
Porphyria cutanea tarda (PCT) is an inherited or acquired decrease in function of uroporphyrinogen decarboxylase (UROD), an enzyme in the heme biosynthetic pathway. In the acquired form, UROD function is decreased within hepatocytes only, while in the inherited form, UROD function is decreased within all tissue.1 The acquired form results from insults to the liver, including infections (eg, hepatitis C virus [HCV], human immunodeficiency virus [HIV]) and various toxins (eg, alcohol, excess iron in hemochromatosis and estrogen), which produce hepatotoxic reactive oxygen species.2-6 Without UROD function, uroporphyrin accumulates within the plasma and can become photoactivated by absorbed ultraviolet A (UVA) light in sun-exposed sites. Cutaneous manifestations result in tissue damage by photoactivated uroporphyrin.1,7 Patients present with photosensitivity, skin fragility, episodic blistering and scars in sun-exposed areas (see Figure 1). Additionally, more subtle features of facial hypertrichosis, scarring alopecia and sclerodermoid changes can be seen (see Figures 2 and 3).7 Twenty-four hour urine analysis shows elevated total poryphrins, composed predominately by uroporyphrins. Histologic examination shows sub-epidermal, cell-poor blisters. Direct immunofluorescence (DIF) demonstrates immunoglobulins (mainly IgG) around blood vessels of the papillary dermis.8
Differential Diagnosis
The differential diagnosis included porphyria cutanea tarda (PCT), pseudoporphyria, localized bullous pemphigoid (BP), bullous impetigo, herpes simplex virus, phototoxic or bullous drug eruption and epidermolysis bullosa acquisita.
Treatment
Patients with PCT should be evaluated for underlying cause, including hepatitis panel, HIV ELISA, serum iron and ferritin. In the case of infection, referral to a hepatologist for treatment of hepatitis or to an infectious disease specialist for treatment of HIV is appropriate.2,5,9 Additionally, triggering factors such as alcohol ingestion and estrogen therapy should be avoided.4,6 In the setting of iron overload, repeated phlebotomy, with a therapeutic goal to reduce ferritin levels to the lower limit of the reference range over 12 to 18 months, will reduce iron-induced inhibition of UROD activity.5,9 Another therapeutic option is antimalarials, which are thought to accelerate secretion of poryphrins. Standard therapy is 200 mg of hydroxychloroquine twice weekly.10 UV light avoidance and sun protection should also be encouraged.3,7
Our Patient
 A definitive diagnosis of localized bullous pemphigoid (BP)-triggered PCT was made in our patient by two 4-mm punch biopsies of the bullae and peri-bullae skin. Biopsy revealed a cell-poor, sub-epidermal blister (see Figure 4, top); DIF revealed 3+ linear IgG and C3 localized to the roof diagnostic of BP (see Figure 5, bottom). A 24-hour urine collection demonstrated elevated total porphyrins majority composed of uroporphyrins
 (1606 mg/L). Serology proved positive for HCV. The patient was referred to a hepatologist for staging and treatment of HCV with combination of pegylated-interferon, ribavirin and boceprevir. The patient was also treated with clobetesol 0.05% ointment twice daily applied to the dorsal hands. Duration of HCV therapy is based on response at 8, 12 and 24 weeks. After the patient completes this regimen, she will follow up with dermatologists for continued treatment of localized BP lesions and initiation of hydroxychloroquine therapy.
Damage of basement membrane zone due to PCT likely exposed antigens capable of triggering this localized BP autoimmune response.11 Similarly, other localized BP variants limited to peristomal and post-irradiation sites have been described.12,13
This case represents an example of epitope sensitization.11 Appropriate treatment to minimize further epitope sensitization is to treat the cause of inflammation to the dermal-epidermal junction (PCT, in this patient’s case) and to suppress autoimmune response locally with topical corticosteroids. If autoimmune blistering extends to beyond localized area, then systemic immunosuppression should be considered.
Dr. Dougherty is a resident in the Texas Tech Department of Dermatology in Lubbock, TX.
Dr. Smith is the attending physician in the Texas Tech Department of Dermatology in Lubbock, TX.
Dr. Khachemoune, the Section Editor of Derm DX, is with the Department of Dermatology, State University of New York, Brooklyn, NY.
Disclosure: The authors have no conflicts of interest or financial disclosures to report.
Patient Presentation
A 46-year-old female presented with painful blisters on her dorsal hands. She reported two previous similar episodes but denied other medical problems aside from perimenopausal symptoms treated with estrogen hormone therapy. On physical examination, the patient had erythematous, flaccid bullae localized to the dorsal hands, bilaterally (see Figure 1). She also had fine hypertrichosis of her temples and preauricular cheeks. She had subtle sclerodermoid changes including perioral rhytids and she appeared older than age stated (see Figures 2 and 3).


 Figures 1-3, left to right
Click on the image to see a larger version.
Figure 1. Bilateral flaccid bullae of dorsal hands.
Figure 2. Preauricular hypertrichosis.
Figure 3. Subtle perioral rhytids.
Two 4-millimeter punch biopsies were obtained and submitted for hematoxylin and eosin stain (H&E) and direct immunofluorescence (DIF) in addition to bacterial and viral cultures.
WHAT IS YOUR DIAGNOSIS?
Porphyria cutanea tarda (PCT) is an inherited or acquired decrease in function of uroporphyrinogen decarboxylase (UROD), an enzyme in the heme biosynthetic pathway. In the acquired form, UROD function is decreased within hepatocytes only, while in the inherited form, UROD function is decreased within all tissue.1 The acquired form results from insults to the liver, including infections (eg, hepatitis C virus [HCV], human immunodeficiency virus [HIV]) and various toxins (eg, alcohol, excess iron in hemochromatosis and estrogen), which produce hepatotoxic reactive oxygen species.2-6 Without UROD function, uroporphyrin accumulates within the plasma and can become photoactivated by absorbed ultraviolet A (UVA) light in sun-exposed sites. Cutaneous manifestations result in tissue damage by photoactivated uroporphyrin.1,7 Patients present with photosensitivity, skin fragility, episodic blistering and scars in sun-exposed areas (see Figure 1). Additionally, more subtle features of facial hypertrichosis, scarring alopecia and sclerodermoid changes can be seen (see Figures 2 and 3).7 Twenty-four hour urine analysis shows elevated total poryphrins, composed predominately by uroporyphrins. Histologic examination shows sub-epidermal, cell-poor blisters. Direct immunofluorescence (DIF) demonstrates immunoglobulins (mainly IgG) around blood vessels of the papillary dermis.8
Differential Diagnosis
The differential diagnosis included porphyria cutanea tarda (PCT), pseudoporphyria, localized bullous pemphigoid (BP), bullous impetigo, herpes simplex virus, phototoxic or bullous drug eruption and epidermolysis bullosa acquisita.
Treatment
Patients with PCT should be evaluated for underlying cause, including hepatitis panel, HIV ELISA, serum iron and ferritin. In the case of infection, referral to a hepatologist for treatment of hepatitis or to an infectious disease specialist for treatment of HIV is appropriate.2,5,9 Additionally, triggering factors such as alcohol ingestion and estrogen therapy should be avoided.4,6 In the setting of iron overload, repeated phlebotomy, with a therapeutic goal to reduce ferritin levels to the lower limit of the reference range over 12 to 18 months, will reduce iron-induced inhibition of UROD activity.5,9 Another therapeutic option is antimalarials, which are thought to accelerate secretion of poryphrins. Standard therapy is 200 mg of hydroxychloroquine twice weekly.10 UV light avoidance and sun protection should also be encouraged.3,7
Our Patient
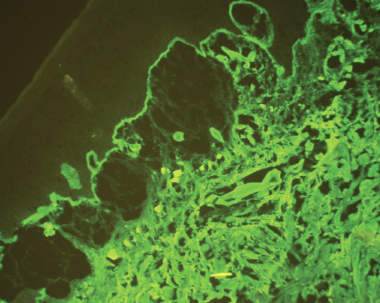
 A definitive diagnosis of localized bullous pemphigoid (BP)-triggered PCT was made in our patient by two 4-mm punch biopsies of the bullae and peri-bullae skin. Biopsy revealed a cell-poor, sub-epidermal blister (see Figure 4, top); DIF revealed 3+ linear IgG and C3 localized to the roof diagnostic of BP (see Figure 5, bottom). A 24-hour urine collection demonstrated elevated total porphyrins majority composed of uroporphyrins
 (1606 mg/L). Serology proved positive for HCV. The patient was referred to a hepatologist for staging and treatment of HCV with combination of pegylated-interferon, ribavirin and boceprevir. The patient was also treated with clobetesol 0.05% ointment twice daily applied to the dorsal hands. Duration of HCV therapy is based on response at 8, 12 and 24 weeks. After the patient completes this regimen, she will follow up with dermatologists for continued treatment of localized BP lesions and initiation of hydroxychloroquine therapy.
Damage of basement membrane zone due to PCT likely exposed antigens capable of triggering this localized BP autoimmune response.11 Similarly, other localized BP variants limited to peristomal and post-irradiation sites have been described.12,13
This case represents an example of epitope sensitization.11 Appropriate treatment to minimize further epitope sensitization is to treat the cause of inflammation to the dermal-epidermal junction (PCT, in this patient’s case) and to suppress autoimmune response locally with topical corticosteroids. If autoimmune blistering extends to beyond localized area, then systemic immunosuppression should be considered.
Dr. Dougherty is a resident in the Texas Tech Department of Dermatology in Lubbock, TX.
Dr. Smith is the attending physician in the Texas Tech Department of Dermatology in Lubbock, TX.
Dr. Khachemoune, the Section Editor of Derm DX, is with the Department of Dermatology, State University of New York, Brooklyn, NY.
Disclosure: The authors have no conflicts of interest or financial disclosures to report.
Patient Presentation
A 46-year-old female presented with painful blisters on her dorsal hands. She reported two previous similar episodes but denied other medical problems aside from perimenopausal symptoms treated with estrogen hormone therapy. On physical examination, the patient had erythematous, flaccid bullae localized to the dorsal hands, bilaterally (see Figure 1). She also had fine hypertrichosis of her temples and preauricular cheeks. She had subtle sclerodermoid changes including perioral rhytids and she appeared older than age stated (see Figures 2 and 3).
Figures 1-3, left to right
Click on the image to see a larger version.
Figure 1. Bilateral flaccid bullae of dorsal hands.
Figure 2. Preauricular hypertrichosis.
Figure 3. Subtle perioral rhytids.
Two 4-millimeter punch biopsies were obtained and submitted for hematoxylin and eosin stain (H&E) and direct immunofluorescence (DIF) in addition to bacterial and viral cultures.
WHAT IS YOUR DIAGNOSIS?
Porphyria cutanea tarda (PCT) is an inherited or acquired decrease in function of uroporphyrinogen decarboxylase (UROD), an enzyme in the heme biosynthetic pathway. In the acquired form, UROD function is decreased within hepatocytes only, while in the inherited form, UROD function is decreased within all tissue.1 The acquired form results from insults to the liver, including infections (eg, hepatitis C virus [HCV], human immunodeficiency virus [HIV]) and various toxins (eg, alcohol, excess iron in hemochromatosis and estrogen), which produce hepatotoxic reactive oxygen species.2-6 Without UROD function, uroporphyrin accumulates within the plasma and can become photoactivated by absorbed ultraviolet A (UVA) light in sun-exposed sites. Cutaneous manifestations result in tissue damage by photoactivated uroporphyrin.1,7 Patients present with photosensitivity, skin fragility, episodic blistering and scars in sun-exposed areas (see Figure 1). Additionally, more subtle features of facial hypertrichosis, scarring alopecia and sclerodermoid changes can be seen (see Figures 2 and 3).7 Twenty-four hour urine analysis shows elevated total poryphrins, composed predominately by uroporyphrins. Histologic examination shows sub-epidermal, cell-poor blisters. Direct immunofluorescence (DIF) demonstrates immunoglobulins (mainly IgG) around blood vessels of the papillary dermis.8
Differential Diagnosis
The differential diagnosis included porphyria cutanea tarda (PCT), pseudoporphyria, localized bullous pemphigoid (BP), bullous impetigo, herpes simplex virus, phototoxic or bullous drug eruption and epidermolysis bullosa acquisita.
Treatment
Patients with PCT should be evaluated for underlying cause, including hepatitis panel, HIV ELISA, serum iron and ferritin. In the case of infection, referral to a hepatologist for treatment of hepatitis or to an infectious disease specialist for treatment of HIV is appropriate.2,5,9 Additionally, triggering factors such as alcohol ingestion and estrogen therapy should be avoided.4,6 In the setting of iron overload, repeated phlebotomy, with a therapeutic goal to reduce ferritin levels to the lower limit of the reference range over 12 to 18 months, will reduce iron-induced inhibition of UROD activity.5,9 Another therapeutic option is antimalarials, which are thought to accelerate secretion of poryphrins. Standard therapy is 200 mg of hydroxychloroquine twice weekly.10 UV light avoidance and sun protection should also be encouraged.3,7
Our Patient
A definitive diagnosis of localized bullous pemphigoid (BP)-triggered PCT was made in our patient by two 4-mm punch biopsies of the bullae and peri-bullae skin. Biopsy revealed a cell-poor, sub-epidermal blister (see Figure 4, top); DIF revealed 3+ linear IgG and C3 localized to the roof diagnostic of BP (see Figure 5, bottom). A 24-hour urine collection demonstrated elevated total porphyrins majority composed of uroporphyrins (1606 mg/L). Serology proved positive for HCV. The patient was referred to a hepatologist for staging and treatment of HCV with combination of pegylated-interferon, ribavirin and boceprevir. The patient was also treated with clobetesol 0.05% ointment twice daily applied to the dorsal hands. Duration of HCV therapy is based on response at 8, 12 and 24 weeks. After the patient completes this regimen, she will follow up with dermatologists for continued treatment of localized BP lesions and initiation of hydroxychloroquine therapy.
Damage of basement membrane zone due to PCT likely exposed antigens capable of triggering this localized BP autoimmune response.11 Similarly, other localized BP variants limited to peristomal and post-irradiation sites have been described.12,13
This case represents an example of epitope sensitization.11 Appropriate treatment to minimize further epitope sensitization is to treat the cause of inflammation to the dermal-epidermal junction (PCT, in this patient’s case) and to suppress autoimmune response locally with topical corticosteroids. If autoimmune blistering extends to beyond localized area, then systemic immunosuppression should be considered.
Dr. Dougherty is a resident in the Texas Tech Department of Dermatology in Lubbock, TX.
Dr. Smith is the attending physician in the Texas Tech Department of Dermatology in Lubbock, TX.
Dr. Khachemoune, the Section Editor of Derm DX, is with the Department of Dermatology, State University of New York, Brooklyn, NY.
Disclosure: The authors have no conflicts of interest or financial disclosures to report.










 Figures 1-3, left to right
 A definitive diagnosis of localized bullous pemphigoid (BP)-triggered PCT was made in our patient by two 4-mm punch biopsies of the bullae and peri-bullae skin. Biopsy revealed a cell-poor, sub-epidermal blister (see Figure 4, top); DIF revealed 3+ linear IgG and C3 localized to the roof diagnostic of BP (see Figure 5, bottom). A 24-hour urine collection demonstrated elevated total porphyrins majority composed of uroporphyrins
 (1606 mg/L). Serology proved positive for HCV. The patient was referred to a hepatologist for staging and treatment of HCV with combination of pegylated-interferon, ribavirin and boceprevir. The patient was also treated with clobetesol 0.05% ointment twice daily applied to the dorsal hands. Duration of HCV therapy is based on response at 8, 12 and 24 weeks. After the patient completes this regimen, she will follow up with dermatologists for continued treatment of localized BP lesions and initiation of hydroxychloroquine therapy.