










Beyond a Single Pathway: Challenging Simplified Views of Psoriasis Biology
Through 3 focused questions, explore how the IL-23/IL-17 axis fits within the broader inflammatory network, how keratinocytes participate in reciprocal inflammatory signaling, and what biological heterogeneity may mean for individualized treatment selection.
Adding Context to an Increasingly Complex Biological Picture
Advances in psoriasis immunology have identified several pathways and cell populations with important roles in disease pathogenesis. Psoriasis is characterized less as a simple linear cascade and more as a dynamic network of interacting immune and tissue processes, sustained by ongoing crosstalk between keratinocytes and immune cells.1,2 Three questions help put that complexity into context.
Question 1: How Does the IL-23/IL-17 Axis Fit Within the Broader Psoriasis Inflammatory Network?
The interleukin (IL)-23/IL-17 axis is central to psoriasis pathogenesis. Activation of plasmacytoid dendritic cells promotes the maturation of myeloid dendritic cells and their production of IL-23.2 Langerhans cells, dendritic cells, and monocytes or macrophages release IL-23 when an inflammatory or biochemical insult reaches the skin.3 T helper 17 (Th17) cells depend on continued IL-23 signaling to persist and expand, and the phenotype is lost when IL-23 is withdrawn.3 When the resulting cytokines, particularly IL-17, activate keratinocytes, those cells produce antimicrobial peptides, cytokines, and chemokines that increase inflammation.2
The axis does not act in isolation. Inflammation centered on the IL-23/IL-17 axis and the tumor necrosis factor (TNF) pathways recruits additional immune cells, such as neutrophils and macrophages, to the dermis and epidermis, augmenting the cycle.1 IL-22, produced mostly by cluster of differentiation 4 positive (CD4+) T cells and group 3 innate lymphoid cells after IL-23, acts on keratinocytes to promote chemokine and antimicrobial peptide production.2
What to Remember: The IL-23/IL-17 axis is central to psoriasis pathogenesis, but its activity occurs within a broader, interconnected inflammatory network.
Question 2: How Do Keratinocytes Shape—and Respond to—the Inflammatory Environment in Psoriasis?
Keratinocytes respond to inflammatory signals and also contribute to them, participating in both the initiation and the maintenance of psoriatic inflammation.2 Immune-derived signals, including TNF-α, interferon-gamma (IFN-γ), IL-17A, and IL-22, stimulate keratinocytes and set off several signaling pathways,2 prompting rapid proliferation and the epidermal thickening, parakeratosis, and impaired differentiation characteristic of plaque disease.1
Activated keratinocytes then, in turn, act on the inflammatory environment. They produce chemokines such as chemokine (C-X-C motif) ligand 8 (CXCL8) and C-C motif chemokine 20 (CCL20) that recruit neutrophils, Th17 cells, and dendritic cells alongside cytokines, antimicrobial peptides such as LL37, and other mediators, amplifying inflammation in a feed-forward cycle.2 S100 calcium-binding protein A8 (S100A8) and S100A9 are released during cellular stress or tissue damage and act as alarmins, and IL-17A and IL-17F strongly induce their expression in keratinocytes.4 Stressed keratinocytes also release self-nucleotides and antimicrobial peptides that aid plasmacytoid dendritic cell activation.2
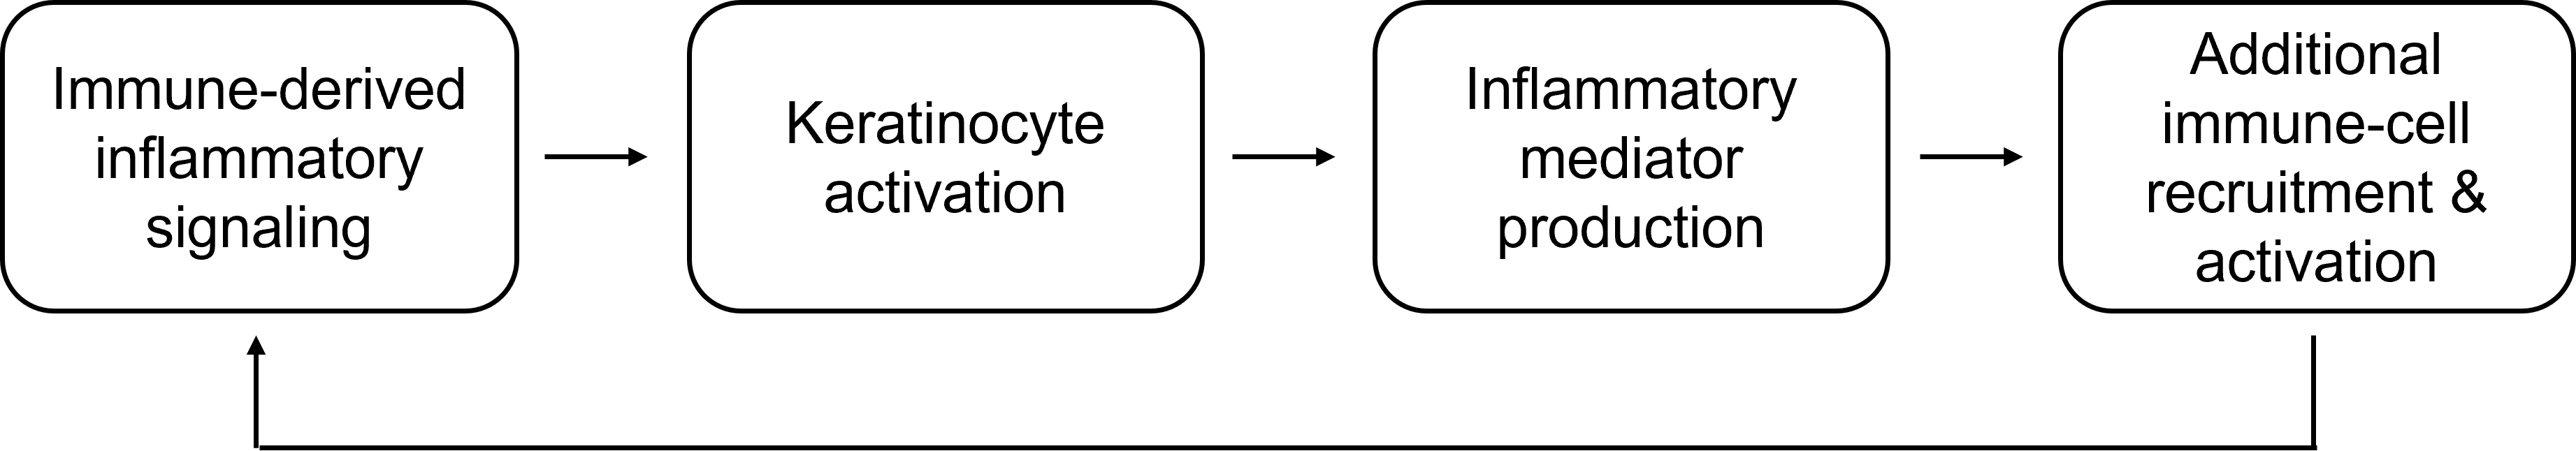
Click image to expand.
What to Remember: Reciprocal signaling between keratinocytes and immune cells contributes to the amplification and persistence of psoriatic inflammation.
Question 3: What Does Biological Heterogeneity Mean for Individualized Treatment Selection?
Emerging research continues to characterize heterogeneity within psoriasis biology. Transcriptomic approaches, including single-cell and spatial RNA sequencing, have resolved major myeloid and T-cell subsets in psoriatic skin, along with fibroblast subpopulations that transition to a pro-inflammatory state.5 Genetic susceptibility also contributes to psoriasis heterogeneity; numerous susceptibility loci have been identified, including a major association within the psoriasis susceptibility 1 (PSORS1) region.6 Differences in gene expression have also been described between responders and non-responders, and human leukocyte antigen (HLA)-C*06:02 has shown inconsistent associations with response across agents.7
These differences may contribute to variation in clinical phenotype, disease course, and treatment response. Clinically, both primary and secondary lack of efficacy can occur despite targeted therapy.7 Demonstrating biological heterogeneity, however, is not the same as having clinically validated predictive biomarkers. Candidate biomarkers and potential endotypes are under investigation, but findings remain heterogeneous and have not yet translated into validated tools for routine treatment selection.7 A recent systematic review and meta-analysis found that recurrent exploratory signals for downstream IL-23/Th17 biomarkers remain hypothesis-generating, with no soluble circulating biomarker sufficiently validated for routine treatment selection.8 Routine molecular profiling, therefore, does not yet allow clinicians to determine reliably which therapy or mechanism will work best for an individual patient.
Individualized treatment decisions still rest on established clinical considerations. Management is guided by disease severity, body surface area involvement, quality-of-life impact, and comorbidities.1 Severity classification increasingly integrates involvement of sensitive sites and treatment history as well,9 and patient preference in the treatment decision-making process is a further consideration.10
What to Remember: Biological heterogeneity may help explain variability among patients, but its translation into validated tools for individualized treatment selection remains an evolving area.
From Biological Complexity to Clinical Context
Psoriasis biology can be read at three levels: an interconnected inflammatory network, reciprocal signaling between immune cells and keratinocytes, and heterogeneity among patients. An increasingly detailed understanding at each level provides context for the variability clinicians observe. Important gaps remain between characterizing that complexity and using it prospectively to guide treatment for individual patients.
References
- Mehta S, Sathe NC. Plaque psoriasis. In: StatPearls. StatPearls Publishing; 2026. Updated September 14, 2025. https://www.ncbi.nlm.nih.gov/books/NBK430879/
- Chakith MRS, Pradeep S, Gangadhar M, et al. Advancements in understanding and treating psoriasis: a comprehensive review of pathophysiology, diagnosis, and therapeutic approaches. PeerJ. 2025;13:e19325. doi:org/10.7717/peerj.19325
- Gooderham MJ, Papp KA, Lynde CW. Shifting the focus - the primary role of IL-23 in psoriasis and other inflammatory disorders. J Eur Acad Dermatol Venereol. 2018;32(7):1111-1119. doi:org/10.1111/jdv.14868
- Christmann C, Zenker S, Martens L, et al. Interleukin 17 promotes expression of alarmins S100A8 and S100A9 during the inflammatory response of keratinocytes. Front Immunol. 2021;11:599947. doi:10.3389/fimmu.2020.599947
- Ma F, Plazyo O, Billi AC, et al. Single cell and spatial sequencing define processes by which keratinocytes and fibroblasts amplify inflammatory responses in psoriasis. Nat Commun. 2023;14(1):3455. doi:10.1038/s41467-023-39020-4
- Langley RGB, Krueger GG, Griffiths CEM. Psoriasis: epidemiology, clinical features, and quality of life. Ann Rheum Dis. 2005;64(suppl 2):ii18-ii23. doi:10.1136/ard.2004.033217
- Camela E, Potestio L, Ruggiero A, Ocampo-Garza SS, Fabbrocini G, Megna M. Towards personalized medicine in psoriasis: current progress. Psoriasis (Auckl). 2022;12:231-250. doi:10.2147/PTT.S328460
- Villa-Gonzalez JM, Arevalo-Ortega I, Gonzalez-Hermosa MR, et al. Potential blood biomarkers predicting treatment response in psoriasis: a systematic review and meta-analysis. J Clin Med. 2026;15(15):6096. doi:10.3390/jcm15156096
- Lupulescu AM, Savu AP, Bucur Ş, Şerban ED, Popescu S, Constantin MM. Hard-to-treat areas in psoriasis: an underevaluated part of the disease. Life (Basel). 2025;15(3):425. doi:10.3390/life15030425
- Esposito M, Giunta A, Gisondi P, et al. Satisfaction and attitudes toward systemic treatments for psoriasis: a cross-sectional study. Dermatol Ther. 2021;34(3):e14949. doi:10.1111/dth.14949
© 2026 HMP Global. All Rights Reserved.




