Biologic Decision-Making for Moderate-to-Severe Atopic Dermatitis
Clinical Summary
Moderate-to-Severe Atopic Dermatitis: Individualizing Systemic Therapy and Supporting Adherence
• Moderate-to-severe atopic dermatitis treatment escalation should reflect clinical signs, body surface area, lichenification, scratching, itch, sleep, concentration, daily activities, and disease burden over time—not a single office examination.
• Biologic and oral JAK inhibitor selection should incorporate age, comorbidities, itch predominance, affected body areas, morphology, and patient preference for injectable versus oral treatment. Shared decision-making can help individualize therapy.
• Treatment expectations should be established before initiation, including anticipated time to symptom improvement and peak efficacy. Clear counseling may support adherence and reduce premature treatment switching.
Reviewed by Jessica Garlewicz, Managing Digital Editor of Immunology Group
Individualized management of moderate-to-severe atopic dermatitis should consider overall disease burden, patient-specific factors and preferences, and clear treatment expectations to guide systemic therapy selection and support adherence.
Transcript
Hi, everybody. I'm Lisa Swanson. I'm a dermatologist and pediatric dermatologist in Boise, Idaho. I work at Ada West Dermatology, and I'm affiliated with St. Luke's Children's Hospital.
What clinical factors signal that it may be time to escalate therapy for patients with moderate-to-severe atopic dermatitis?
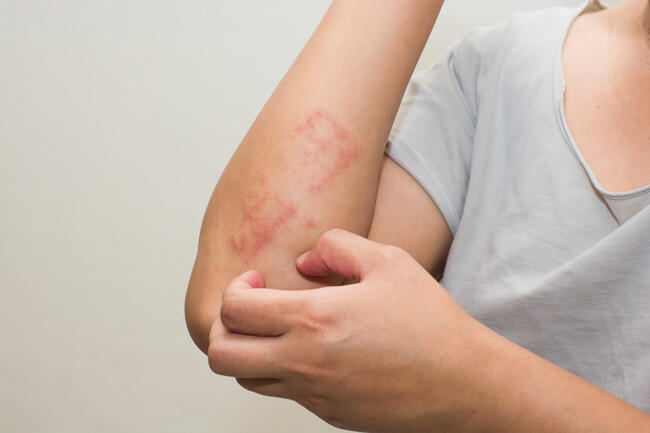
Dr Swanson: I think there are so many things that go into choosing whether a patient is ready to either escalate therapy to a systemic agent or perhaps change therapies from one systemic to another. Of course, there’s taking a look at them in the exam room. How’s their skin looking? What’s the body surface area that their atopic dermatitis is taking up? How much lichenification and signs of scratching do they have?
So, it’s the clinical signs and symptoms, but it’s also having a conversation with the patient and their family about how things are going. When you see that patient in your clinic exam room, you’re catching them at one moment in time. It could be the best day they’ve had over the past 2 to 3 months. So, if all that you do is take a look, you’re missing a huge part of the picture. Talk to them about how things have been going.
Is today a good day, a bad day, a medium day? How are things going with sleep, with itch, with focus during the day? What activities is the patient doing or not doing? Are they not going to sleepovers because they’re too itchy and uncomfortable? Are they not playing sports because they don’t want to wear the uniform that might expose their arms or their legs?
So, we have to jumble all of that together: the way a person looks in clinic and an assessment of their disease signs and symptoms, but also how they are experiencing the condition and how things have been going over the longer haul, not just at that one moment in time.
With multiple biologic therapies available for atopic dermatitis, how do you differentiate among treatment options and select the most appropriate therapy for an individual patient?
Dr Swanson: Yes. For a patient who has atopic dermatitis who’s at least 12 years old, the world is their oyster. We have so many options to choose from in terms of topicals but, most importantly, systemic therapy. We have 4 biologics that are approved for ages 12 and up, one of which is approved down to the age of 6 months, and we have 2 oral JAK inhibitors.
So, any patient out there with moderate-to-severe atopic dermatitis who’s 12 and up should not still be dealing with their condition. We have so many things to choose from, whether you want a shot or a pill. All of these choices are good ones. We really can’t go wrong. I think the biggest mistake we make is undertreating atopic dermatitis. Mentioning the options that exist, I think, is the most vitally important part of the conversation, just so patients know what’s out there.
You might have an initial conversation with a 13-year-old, and they say things are fine. So many 13-year-olds, especially 13-year-old boys, are fine with their topicals, and they say they’re using them just periodically. Then you take a look at their skin, and you talk to them a little bit more, and it becomes very obvious that they’re not fine.
So, you go into a conversation about the options available, and sometimes that 13-year-old said they’re fine because they just didn’t know that there were alternatives. Our patients, despite everything that’s out there on the internet and social media, don’t know about all these options, and they certainly don’t know all the little intricacies of all of these choices unless we take the time to tell them about them. So, I think if you’re a patient with moderate-to-severe atopic dermatitis or you’re caring for a patient with moderate-to-severe AD, there is truly something for everyone.
Breaking down those choices is really, really important. I actually rarely am the one who makes the decision about which therapy we use. I typically am the one telling the patients and their families about them and then letting them choose based on that information.
So, ask about other comorbidities. Say they also have asthma. Well, there’s one biologic that’s also approved to treat asthma, so that might seem appealing. Maybe they also have alopecia areata or vitiligo or some condition that would benefit from a JAK inhibitor. If I’m able to treat 2 conditions at once, I use the expression, “If I’m able to feed 2 birds with one scone—we’re not killing birds with stones anymore; we’re feeding birds with scones.” If I’m able to treat 2 things at once, wonderful. What an efficient way to make the patient’s life better.
So, have that conversation about their preferences, what comorbidities you might be dealing with, and their opinions on a shot versus a pill.
All of these things really factor in. You also might have a solid discussion about itch. We know that patients with atopic dermatitis are itchy, but how itch-predominant are they? What body surface areas are the most affected, and what is the morphology of those areas? We’ve learned that patients with psoriasis-eczema overlap features tend to respond best to an oral JAK inhibitor. We can take all of these little clues and guide our patients toward the therapy that’s going to best help them.
I think the other unexpected benefit that comes from explaining all these choices is that if the family chooses one thing and it doesn’t work as well as we want it to, they don’t lose hope because they know there are all sorts of other things they could try instead. So, it preserves the hope and the belief that we can make them better.
Even if the first thing doesn’t work, we can go on to the second thing. Nobody in this era needs to be living with moderate-to-severe atopic dermatitis.
What strategies can clinicians use to improve communication with patients and caregivers about treatment expectations, adherence, and long-term disease control?
Dr Swanson: I think there’s a lot that goes into this question. It’s a very good question. I think one of the best ways to get patients to the best outcome is simply going through all the options that are available to them and seeing what resonates most with them.
You’re going to have better outcomes if the patient is the one who says, “Okay, that sounds good to me, and I will be compliant with that treatment because I have chosen it for myself and because it meets my needs the best.”
So, having that shared decision-making, with most of it honestly falling on the patient and their family to choose the one that’s right for them, is one of the biggest parts of it. Then, of course, there’s setting realistic expectations. When should they expect to be looking and feeling better?
That’s a little bit different for each of our options. Some of our options are super, super fast, particularly for itch. Some of our options are wonderful medicines, but they’re a little bit of a slower burn. They just take a little bit more time to ramp up to speed.
So, what can the patient expect from the treatment? When can they expect to look and feel better? I think that’s very important so that you don’t follow up at a month and the patient says, “Oh, it’s just not working for me. I want to switch.”
We need to prepare our patients ahead of time so that they can set realistic expectations and know how long it’s going to take for them to feel better. I heard somebody say something recently that really stuck with me: If you warn somebody about something ahead of time, it’s an explanation. If you tell them about it afterward, it’s an excuse.
So, if you tell them beforehand, “Hey, this medicine tends to reach peak efficacy at about 4 months,” then that gives them some expectations. If you say that when they’re 2 months in and they’re ready to switch, they’re ready to jump ship, and you’re like, “Oh, wait, wait, wait. Let’s just give it another 2 months,” then they’re like, “Why would I? I’m not feeling that improvement yet.” They don’t understand what they should have expected from the treatment.
So, building our patients up for success and educating them on what they can expect from the treatment is going to get you more buy-in. The patient is going to be more consistent and, in the end, happier.