Psoriasis Pearls With Dr Mark Lebwohl: Practical Strategies for Refractory Cases, Combinations, and Cancer Risk
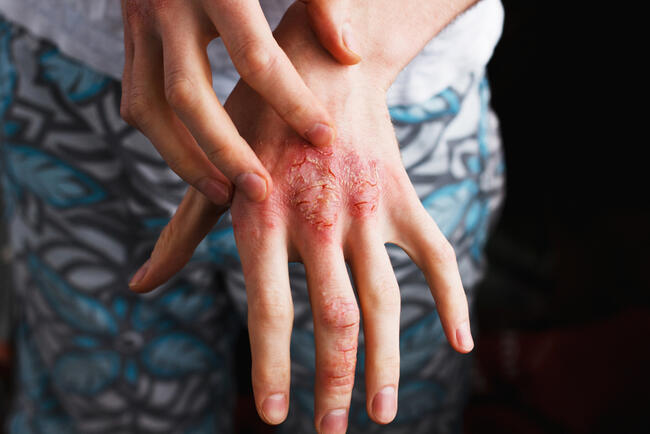
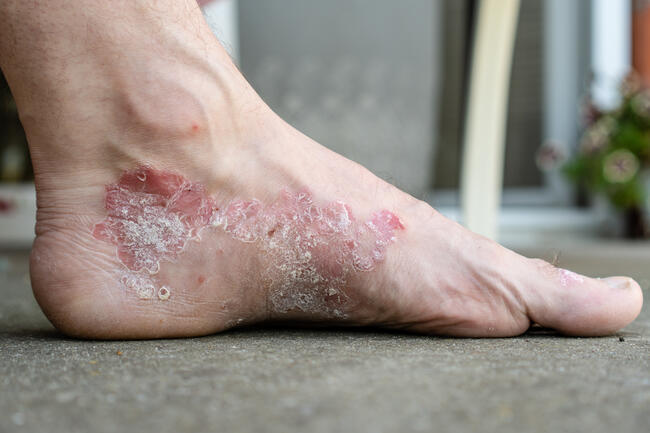
At the Fall Clinical 2025 session, “Psoriasis Pearls That Will Help Your Practice NOW!”, Mark Lebwohl, MD, offered an unfiltered and practical guide to managing difficult psoriasis cases, particularly those who fail multiple lines of therapy. Through patient cases and clinical anecdotes, Dr Lebwohl covered combination therapy, treatment resistance, cancer risk stratification, and drug safety considerations. His message to practicing dermatologists was clear: Rethink the algorithm, tailor treatment, and when needed, challenge the conventional assumptions.
Dr Lebwohl opened with a familiar question: What do you do when a patient fails your best treatment options? For one 28-year-old woman who had failed phototherapy, methotrexate, cyclosporine, and multiple biologics, the answer was combination therapy.
“If your best treatments don’t work, try combinations. Combinations work,” Dr Lebwohl emphasized.
He described combining IL-17 or IL-23 inhibitors with apremilast or TYK2 inhibitors like deucravacitinib. “These are not potent immunosuppressants. You can add them safely,” he explained, even referencing successful appeals to insurers for patients initially denied coverage due to package insert language.
In patients who are overweight and not responding to standard therapy, weight loss itself can be therapeutic. “Have them lose 60 pounds and, lo and behold, they clear,” said Dr Lebwohl. He pointed to glucagon-like peptide-1 agonists as pharmacologic tools to help patients achieve the necessary reduction.
“When you use that combination, psoriasis just melts away. It’s dramatically effective,” he added.
Even in experienced hands, misdiagnosis can happen. Dr Lebwohl described several instances where patients presumed to have psoriasis were eventually diagnosed with pemphigus foliaceus or granuloma annulare after failing multiple biologics.
“When you have a drug as effective as brodalumab and it’s not working, question your diagnosis,” he said.
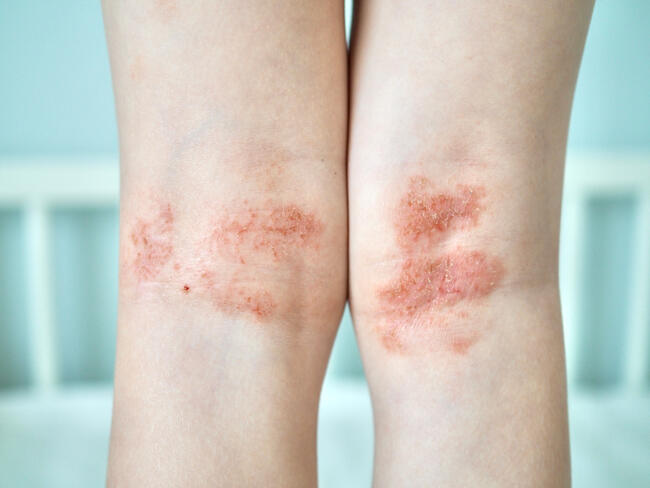
With better psoriasis control comes paradoxical inflammation. Dr Lebwohl discussed the growing recognition of paradoxical eczema in patients treated with IL-17 and IL-23 inhibitors. “You block psoriasis so completely that it changes direction and goes to eczema,” he explained.
In his recent publication of 35 such cases:
- 20 had a history of atopy
- 7 were treated with dupilumab while remaining on their psoriasis biologic with complete remission
- 6 were switched to Janus kinase (JAK) inhibitors, with all but 1 responding well
- Topicals were least effective, working in only 11 of 15 cases
Interestingly, the reverse has also been reported. “Blocking dupilumab can lead to paradoxical psoriasis,” Dr Lebwohl noted, referencing a 58% increase in psoriasis among dupilumab-treated patients in a hazard ratio analysis.
One of the most clinically consequential segments addressed psoriasis management in patients with skin cancer, particularly keratinocyte carcinomas.
Dr Lebwohl reviewed malignancy risk by therapy class:
- Phototherapy (UVB): No increased risk
- Tumor necrosis factor (TNF) inhibitors: Increased risk for nonmelanoma skin cancers, lymphomas, and potentially melanoma
- Methotrexate: Significantly increases cancer risk; has been linked to lymphoma regression after discontinuation
- Cyclosporine: High risk of squamous cell carcinoma (SCC), especially in transplant populations
- JAK inhibitors (non-TYK2): Boxed warning for malignancy
- IL-17 and IL-23 inhibitors: No increase, possibly protective
Dr Lebwohl advised, “If you have a patient with lymphoma and you give them a TNF blocker, you’re nuts.” In contrast, he cited IL-17 and IL-23 inhibitors as the safest biologics, with mouse model data suggesting that IL-23 blockade may inhibit tumor development.
When psoriasis coexists with multiple SCCs, Dr Lebwohl favors acitretin, citing both transplant literature and clinical experience. He presented a case where acitretin cleared both psoriasis and SCCs in an 87-year-old woman.
“Acitretin reduced squamous cell carcinoma frequency by almost 90% in transplant studies,” he said. In another patient, visible squamous tumors resolved after 3 months of high-dose acitretin, confirmed by biopsy.
Dr Lebwohl also highlighted a surprising intervention—the HPV vaccine—in the context of SCC. “It was given intramuscularly and intralesionally,” he said, describing a dramatic response. “We tried it, and the lesion disappeared.”
To close, Dr Lebwohl urged clinicians to download OpenEvidence, a fast drug interaction checker. He shared a final anecdote from a late colleague: “The best drug interaction advice I ever heard: Never prescribe a laxative and a sleeping pill at the same time.”
Reference
Lebwohl M. Psoriasis pearls that will help your practice now. Presented at: 2025 Fall Clinical Dermatology Conference. October 23–26, 2025; Virtual.