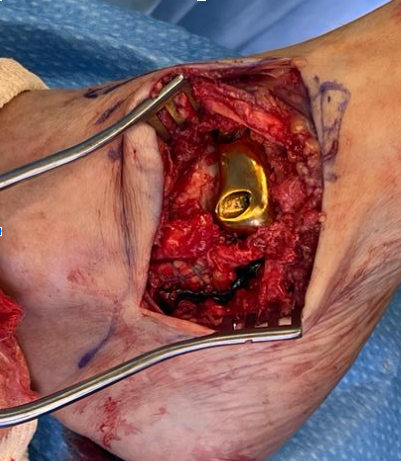
Study: Preoperative Dorsiflexion Predicts Motion After Total Ankle Arthroplasty
A retrospective cohort study evaluated clinical and surgical factors associated with limited weight-bearing dorsiflexion following total ankle arthroplasty. The findings may help foot and ankle surgeons counsel patients more accurately about anticipated postoperative motion and function.
Key Takeaways
- Nearly two-thirds of patients (63.4%) studied demonstrated less than 20 degrees of weight-bearing dorsiflexion at a mean follow-up of 3.3 years.
- Preoperative clinical dorsiflexion was the only significant independent predictor of improved postoperative dorsiflexion.
- Gastrocnemius recession and tendo-Achilles lengthening were not associated with postoperative dorsiflexion in this cohort, while patients achieving full dorsiflexion reported better functional outcomes.
Limited dorsiflexion following total ankle arthroplasty (TAA) has been associated with poorer functional outcomes and lower patient satisfaction. In a recent retrospective cohort study in Foot and Ankle International, researchers examined whether patient characteristics, comorbidities, surgical history, implant variables, or adjunctive procedures could predict limited weight-bearing dorsiflexion after primary TAA.1
The analysis included 175 patients who underwent elective primary TAA by a single surgeon between 2013 and 2023.1 Postoperative range of motion was evaluated using weight-bearing lateral radiographs obtained during maximal dorsiflexion and plantarflexion. The investigators defined limited postoperative dorsiflexion as less than 20 degrees. Preoperative dorsiflexion was determined through clinical assessment.1
Researchers also collected demographic information, medical comorbidities, surgical history, polyethylene insert size, and use of adjunctive procedures, including gastrocnemius recession and tendo-Achilles lengthening. Functional outcomes were assessed using the Foot and Ankle Ability Measure–Activities of Daily Living (FAAM-ADL) subscale.1
Most Patients Had Limited Dorsiflexion After TAA
At a mean follow-up of 3.3 years, 111 patients (63.4%) demonstrated limited postoperative dorsiflexion, while 64 patients (36.6%) achieved at least 20 degrees. Patients in the full-dorsiflexion group were older than those in the limited-dorsiflexion group, with mean ages of 65.5 and 61.5 years, respectively (P=.013).1
Patients who achieved full postoperative dorsiflexion also reported better function. Mean FAAM-ADL scores were 86.9 in the full-dorsiflexion group compared with 70.0 in the limited-dorsiflexion group (P=.010).1
No significant associations emerged between postoperative dorsiflexion and body mass index, weight, tobacco use, diabetes, sex, medical comorbidities, polyethylene size, or adjunctive procedures. Prior open reduction and internal fixation (ORIF) was more common among patients with limited postoperative dorsiflexion; however, it did not remain an independent predictor in the multivariable analysis.1
Preoperative Motion May Inform Patient Counseling
Preoperative clinical dorsiflexion was the only significant independent predictor of improved postoperative dorsiflexion. The authors concluded that careful preoperative assessment may help surgeons counsel patients more accurately regarding anticipated motion following TAA. Establishing realistic expectations may be particularly important given that nearly two-thirds of patients in this cohort did not achieve 20 degrees of postoperative weight-bearing dorsiflexion.1
Reference
- Thomas GM, McCahon JAS, Dulitzki Y, et al. Predictors of limited weight-bearing dorsiflexion following total ankle arthroplasty. Foot Ankle Int. Published online July 6, 2026. doi:10.1177/10711007261457413
© 2026 HMP Global. All Rights Reserved.
Any views and opinions expressed are those of the author(s) and/or participants and do not necessarily reflect the views, policy, or position of Podiatry Today or HMP Global, their employees, and affiliates.