Podiatric Hospitalists: A Practical Inpatient Model for Limb Salvage and High-Value Foot Care
A podiatric hospitalist can provide focused inpatient oversight for patients with complex foot and ankle conditions, helping coordinate timely evaluation, multidisciplinary care, and safe discharge planning. This article explores how the model may strengthen limb salvage pathways while improving hospital efficiency and continuity of care.
Key Takeaways
-
Early podiatric involvement can help distinguish limb-threatening conditions requiring urgent intervention from lower-acuity problems that may be managed safely in the outpatient setting.
-
Podiatric hospitalists can coordinate infection control, perfusion assessment, operative timing, offloading, wound care, and follow-up when multiple specialties are involved.
-
Beyond procedural care, the model may support more efficient resource use, clearer discharge plans, clinician education, and hospital-level quality improvement.
Hospitals are seeing more patients with diabetes, peripheral artery disease (PAD), chronic limb-threatening ischemia (CLTI), infection, trauma, and complex lower extremity wounds. These patients rarely fit into a sole specialty lane. A single admission may involve hospital medicine, vascular surgery, infectious disease, endocrinology, wound care, orthopedics, plastic surgery, rehabilitation, nursing, and discharge planning. In that setting, the foot and ankle problem can become one piece of a much larger inpatient puzzle.
We contend that a podiatric hospitalist may help close that gap. In this model, a board-certified Doctor of Podiatric Medicine is dedicated to the evaluation and management of acutely hospitalized patients with foot and ankle conditions. The goal is not to replace outpatient podiatry or existing surgical services. Rather, the podiatric hospitalist brings focused lower-extremity expertise into the hospital workflow, where delays in diagnosis, source control, offloading, vascular evaluation, and discharge planning can directly affect limb salvage.
Why the Model Matters
Modern PAD and diabetic foot care guidelines emphasize multidisciplinary management.1–3 Patients with diabetes-related foot infection, ischemic wounds, Charcot neuroarthropathy, or tissue loss often need coordinated decisions about infection control, perfusion, operative timing, antibiotics, offloading, and follow-up. When that coordination is fragmented, patients may experience unnecessary admissions, duplicative testing, delayed procedures, unclear ownership of the wound, or unsafe discharge plans.
A podiatric hospitalist can serve as the inpatient point person for foot and ankle pathology. This includes early examination, wound assessment, neurovascular documentation, review of imaging and laboratory data, and triage of acuity. Just as importantly, the podiatric hospitalist can help determine which service should be involved next and when. Some patients need urgent incision and drainage. Some need vascular testing before surgical-level intervention. Others can avoid admission with appropriate local wound care, immobilization or offloading, antibiotics when indicated, and close outpatient follow-up.
Improving ED and Inpatient Triage
The emergency department (ED) is one of the clearest places where we feel this model can add value. Patients may present with diabetic foot infection, ulcer deterioration, Charcot neuroarthropathy, fractures, postoperative concerns, cellulitis, ischemic rest pain, or mixed infectious and vascular findings. Early podiatric input can help distinguish urgent limb-threatening problems from lower-acuity conditions that can be managed safely outside the hospital.
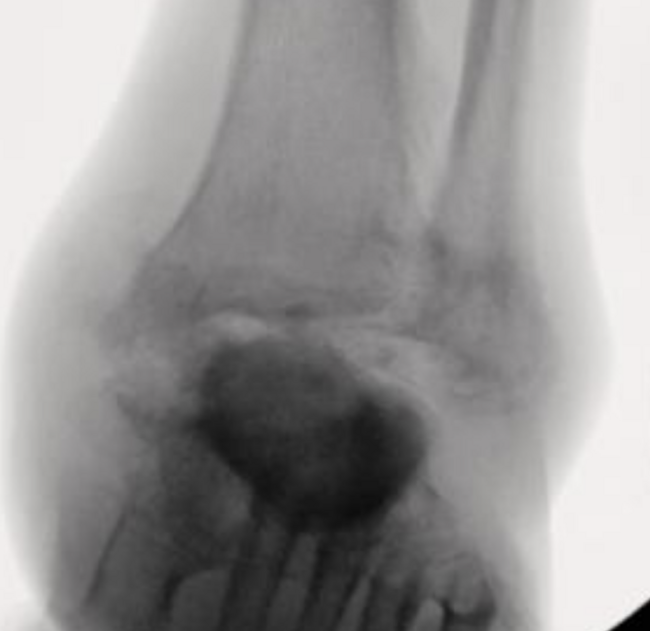
This is especially important for Charcot neuroarthropathy, which may be confused with infection or trauma. Misclassification can lead to unnecessary antibiotics, delayed immobilization, and inappropriate disposition. A podiatric hospitalist can support ED teams by creating practical pathways for imaging, laboratory evaluation, offloading, admission criteria, and outpatient follow-up.
For diabetic foot infections, time matters. Current IWGDF/IDSA guidance recommends urgent surgical consultation for severe infection or moderate infection complicated by gangrene, necrotizing infection, deep abscess, compartment syndrome, or severe ischemia.3 It also recommends considering early surgery within 24 to 48 hours for moderate and severe infections when infected or necrotic tissue must be removed.3 A podiatric hospitalist helps ensure that these cases are identified early and escalated appropriately.
Coordinating Source Control and Perfusion
One of the most important inpatient decisions is whether the foot problem is primarily infectious, ischemic, neuropathic, traumatic, postoperative, or mixed. That distinction changes the next step. A deep-space infection may require urgent source control. An ischemic wound may require noninvasive vascular testing and vascular consultation before major debridement or final amputation-level planning. A neuropathic wound may require offloading and wound care more than broad diagnostic testing.
The podiatric hospitalist can coordinate this sequence. For example, debridement without a perfusion plan may worsen tissue loss in a patient with severe ischemia. Conversely, delaying drainage in the setting of deep infection can increase morbidity and threaten the limb. The podiatric hospitalist can help align debridement, cultures, antibiotics, revascularization timing, wound care, offloading, and postoperative plans.
This coordination is particularly important when multiple services are consulted but no single team is clearly responsible for the foot and ankle plan. The podiatric hospitalist can document wound severity, clarify operative urgency, communicate vascular concerns, and help establish whether the patient needs bedside treatment, urgent surgery, revascularization evaluation, or safe outpatient follow-up.
Value Beyond the Operating Room
The value of this role is not limited to procedures. A dedicated inpatient podiatry service can reduce low-yield imaging, avoid duplicative consultations, and clarify discharge requirements. It can also improve communication with nursing, therapy, case management, and outpatient clinicians.
We find that discharge planning is often where limb salvage succeeds or fails. A patient with a diabetic foot ulcer may leave the hospital with antibiotics but no offloading device, no dressing plan, no vascular follow-up, and no clear warning signs to look out for. A podiatric hospitalist can help ensure that the patient leaves with appropriate initial wound care supplies, footwear or offloading plans, follow-up appointments, and instructions that match the actual diagnosis and risk level.
This model may also improve length of stay. Timely podiatric consultation has been associated with shorter hospitalization and lower readmission in patients admitted with foot and ankle wounds. Multidisciplinary diabetic foot programs have also been associated with improved healing, lower costs, and fewer major amputations.4–8 While every hospital needs to evaluate its own staffing and patient population, the direction is consistent: coordinated foot care is more efficient than fragmented foot care.
The model may also support patient experience. Patients admitted with wounds, fractures, infections, or postoperative complications often receive input from several clinicians, which can make the care plan feel confusing. A podiatric hospitalist can provide focused explanation of the foot diagnosis, expected treatment course, weight-bearing status, wound-care plan, and follow-up needs. That consistency can contribute to improved confidence, adherence, and satisfaction.
Education and Systems Improvement
A podiatric hospitalist can also serve as an educator. This may include teaching residents, medical students, ED clinicians, hospitalists, and nursing teams how to recognize high-risk foot findings, document wounds, identify red flags, and understand when urgent escalation is needed. Over time, the podiatric hospitalist can help build pathways for diabetic foot infection, Charcot neuroarthropathy, inpatient wound care, fracture triage, and postoperative complications.
This systems role matters because many hospital delays are predictable. Common examples include uncertainty about whether a wound needs admission, whether magnetic resonance imaging (MRI) is necessary, whether vascular studies should come before surgery, whether antibiotics should be continued, and whether a patient can safely return home. A podiatric hospitalist can help standardize these decisions while still individualizing care.
A hospital-based podiatry model also creates opportunities for quality improvement. Relevant metrics may include time to consultation, time to source control, time to vascular evaluation, length of stay, readmission, major amputation, discharge with offloading, follow-up completion, and patient satisfaction. Tracking these measures can help hospitals understand where delays occur and whether a podiatric hospitalist improves care delivery.
Fitting Into the Podiatry Ecosystem
The podiatric hospitalist does not need to be a single fixed position in every setting. In some hospitals, the model may be a dedicated employed role. In others, it may be a rotating inpatient coverage system within a group or department. The key feature is not the title, but the function: timely inpatient ownership of foot and ankle pathology, integration with vascular and medical teams, and accountability for the transition from admission to discharge.
This model may also be attractive from a career development standpoint. A podiatric hospitalist role offers regular interaction with multidisciplinary teams, exposure to high-acuity pathology, opportunities for teaching, and a platform for research or quality improvement work. For institutions with podiatry residents or foot and ankle trainees, this role can strengthen inpatient education and create clearer clinical pathways.
As podiatry continues to expand across outpatient, surgical, wound care, and limb salvage settings, the hospital remains a critical site of care for the highest-risk patients. A podiatric hospitalist model offers a practical way to bring podiatric expertise to the point where it may have the greatest immediate impact.
Conclusion
In our observation, the podiatric hospitalist is a timely model for modern inpatient foot and ankle care. By improving triage, coordinating source control and perfusion decisions, reducing unnecessary delays, supporting discharge planning, and strengthening multidisciplinary limb salvage pathways, this role can improve both clinical quality and hospital efficiency. For patients with diabetic foot complications, PAD, infection, trauma, and complex wounds, the podiatric hospitalist may help ensure that the right care happens at the right time.
Drs.Thaqi and Shook practice in the Department of Orthopaedics at the Cleveland Clinic in Cleveland, Ohio.
Drs. Bertolino, Kibrik, and Kirksey practice in the Department of Vascular Surgery at the Heart, Vascular & Thoracic Institute at the Cleveland Clinic in Cleveland, Ohio, where Dr. Kirksey is the Vice Chairman of Vascular Surgery.
References
-
Gornik HL, Aronow HD, Goodney PP, et al. 2024 ACC/AHA/AACVPR/APMA/ABC/SCAI/SVM/SVN/SVS/SIR/VESS Guideline for the management of lower extremity peripheral artery disease: A report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2024;149(24):e1313-e1410.
-
Conte MS, Bradbury AW, Kolh P, et al. Global vascular guidelines on the management of chronic limb-threatening ischemia. J Vasc Surg. 2019;69(6S):3S-125S.e40.
-
Senneville É, Albalawi Z, van Asten SA, et al. IWGDF/IDSA guidelines on the diagnosis and treatment of diabetes-related foot infections (IWGDF/IDSA 2023). Diabetes Metab Res Rev. 2024;40(3):e3687.
-
Kim PJ, Attinger CE, Evans KK, Steinberg JS. Role of the podiatrist in diabetic limb salvage. J Vasc Surg. 2012;56:1168-1172.
-
Joret MO, Osman K, Dean A, et al. Multidisciplinary clinics reduce treatment costs and improve patient outcomes in diabetic foot disease. J Vasc Surg. 2019;70:806-814.
-
Cichero MJ, Bower VM, Walsh TP, Yates BJ. Reducing length of stay for acute diabetic foot episodes using an extended-scope podiatric high-risk foot coordinator. J Foot Ankle Res. 2013;6:47.
-
Musuuza J, Sutherland BL, Kurter S, et al. Multidisciplinary teams to reduce major amputations for patients with diabetic foot ulcers: a systematic review. J Vasc Surg. 2020;71:1433-1446.e3.
-
Behme S, Husain ZS, Santiago Rivera OJ. Impact of podiatric surgery consultation for foot and ankle wounds on patient outcomes in a community hospital. J Foot Ankle Surg. 2023;62:916-921.
© 2026 HMP Global. All Rights Reserved.
Any views and opinions expressed are those of the author(s) and/or participants and do not necessarily reflect the views, policy, or position of Podiatry Today or HMP Global, their employees, and affiliates.