Aortic Valve Replacement in Patients With Small Aortic Annuli: A Systematic Review and Network Meta-Analysis
© 2026 HMP Global. All Rights Reserved.
Any views and opinions expressed are those of the author(s) and/or participants and do not necessarily reflect the views, policy, or position of the Journal of Invasive Cardiology or HMP Global, their employees, and affiliates.
J INVASIVE CARDIOL 2026. doi:10.25270/jic/26.00198. Epub September 24, 2026.
Key Clinical Summary
· A small aortic annulus is a key determinant of hemodynamics, durability, and clinical outcomes after aortic valve intervention.
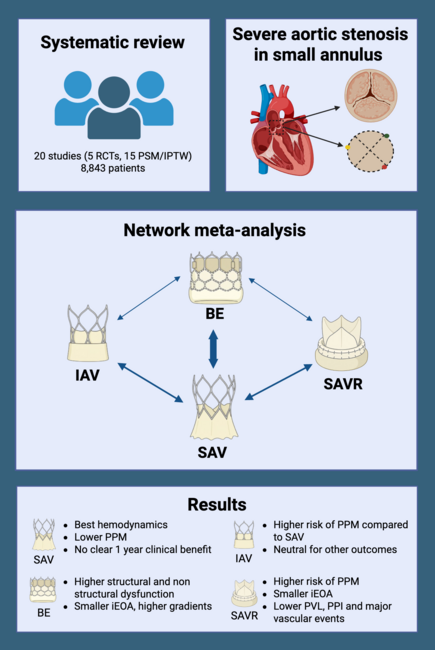
· In a systematic network meta-analysis, supra-annular self-expanding valves were associated with a lower risk of severe prosthesis-patient mismatch than intra-annular devices and surgical aortic valve replacement (SAVR), without differences in 1-year mortality.
· Balloon-expandable valves were associated with increased hemodynamic structural dysfunction. SAVR had the least favorable hemodynamics but lower risks of paravalvular leak, pacemaker implantation, and major vascular complications.
Abstract
Objectives. Up to 40% of patients with aortic stenosis undergoing valve replacement have a small annulus, a key determinant of valve hemodynamics, durability, and clinical outcomes. Surgical and transcatheter approaches have been reported to be determined by prosthesis design, considering the operative mortality and morbidity risk. The authors sought to evaluate surgical and transcatheter strategies in patients with small aortic annuli.
Methods. The authors systematically reviewed and synthesized evidence of 20 studies including 8843 patients. Primary outcomes included all-cause death and severe patient-prosthesis mismatch (PPM). Secondary outcomes included hemodynamic structural and non-structural valve dysfunction, postprocedural hemodynamics (indexed effective orifice area [iEOA] and mean transvalvular gradients), and major clinical events.
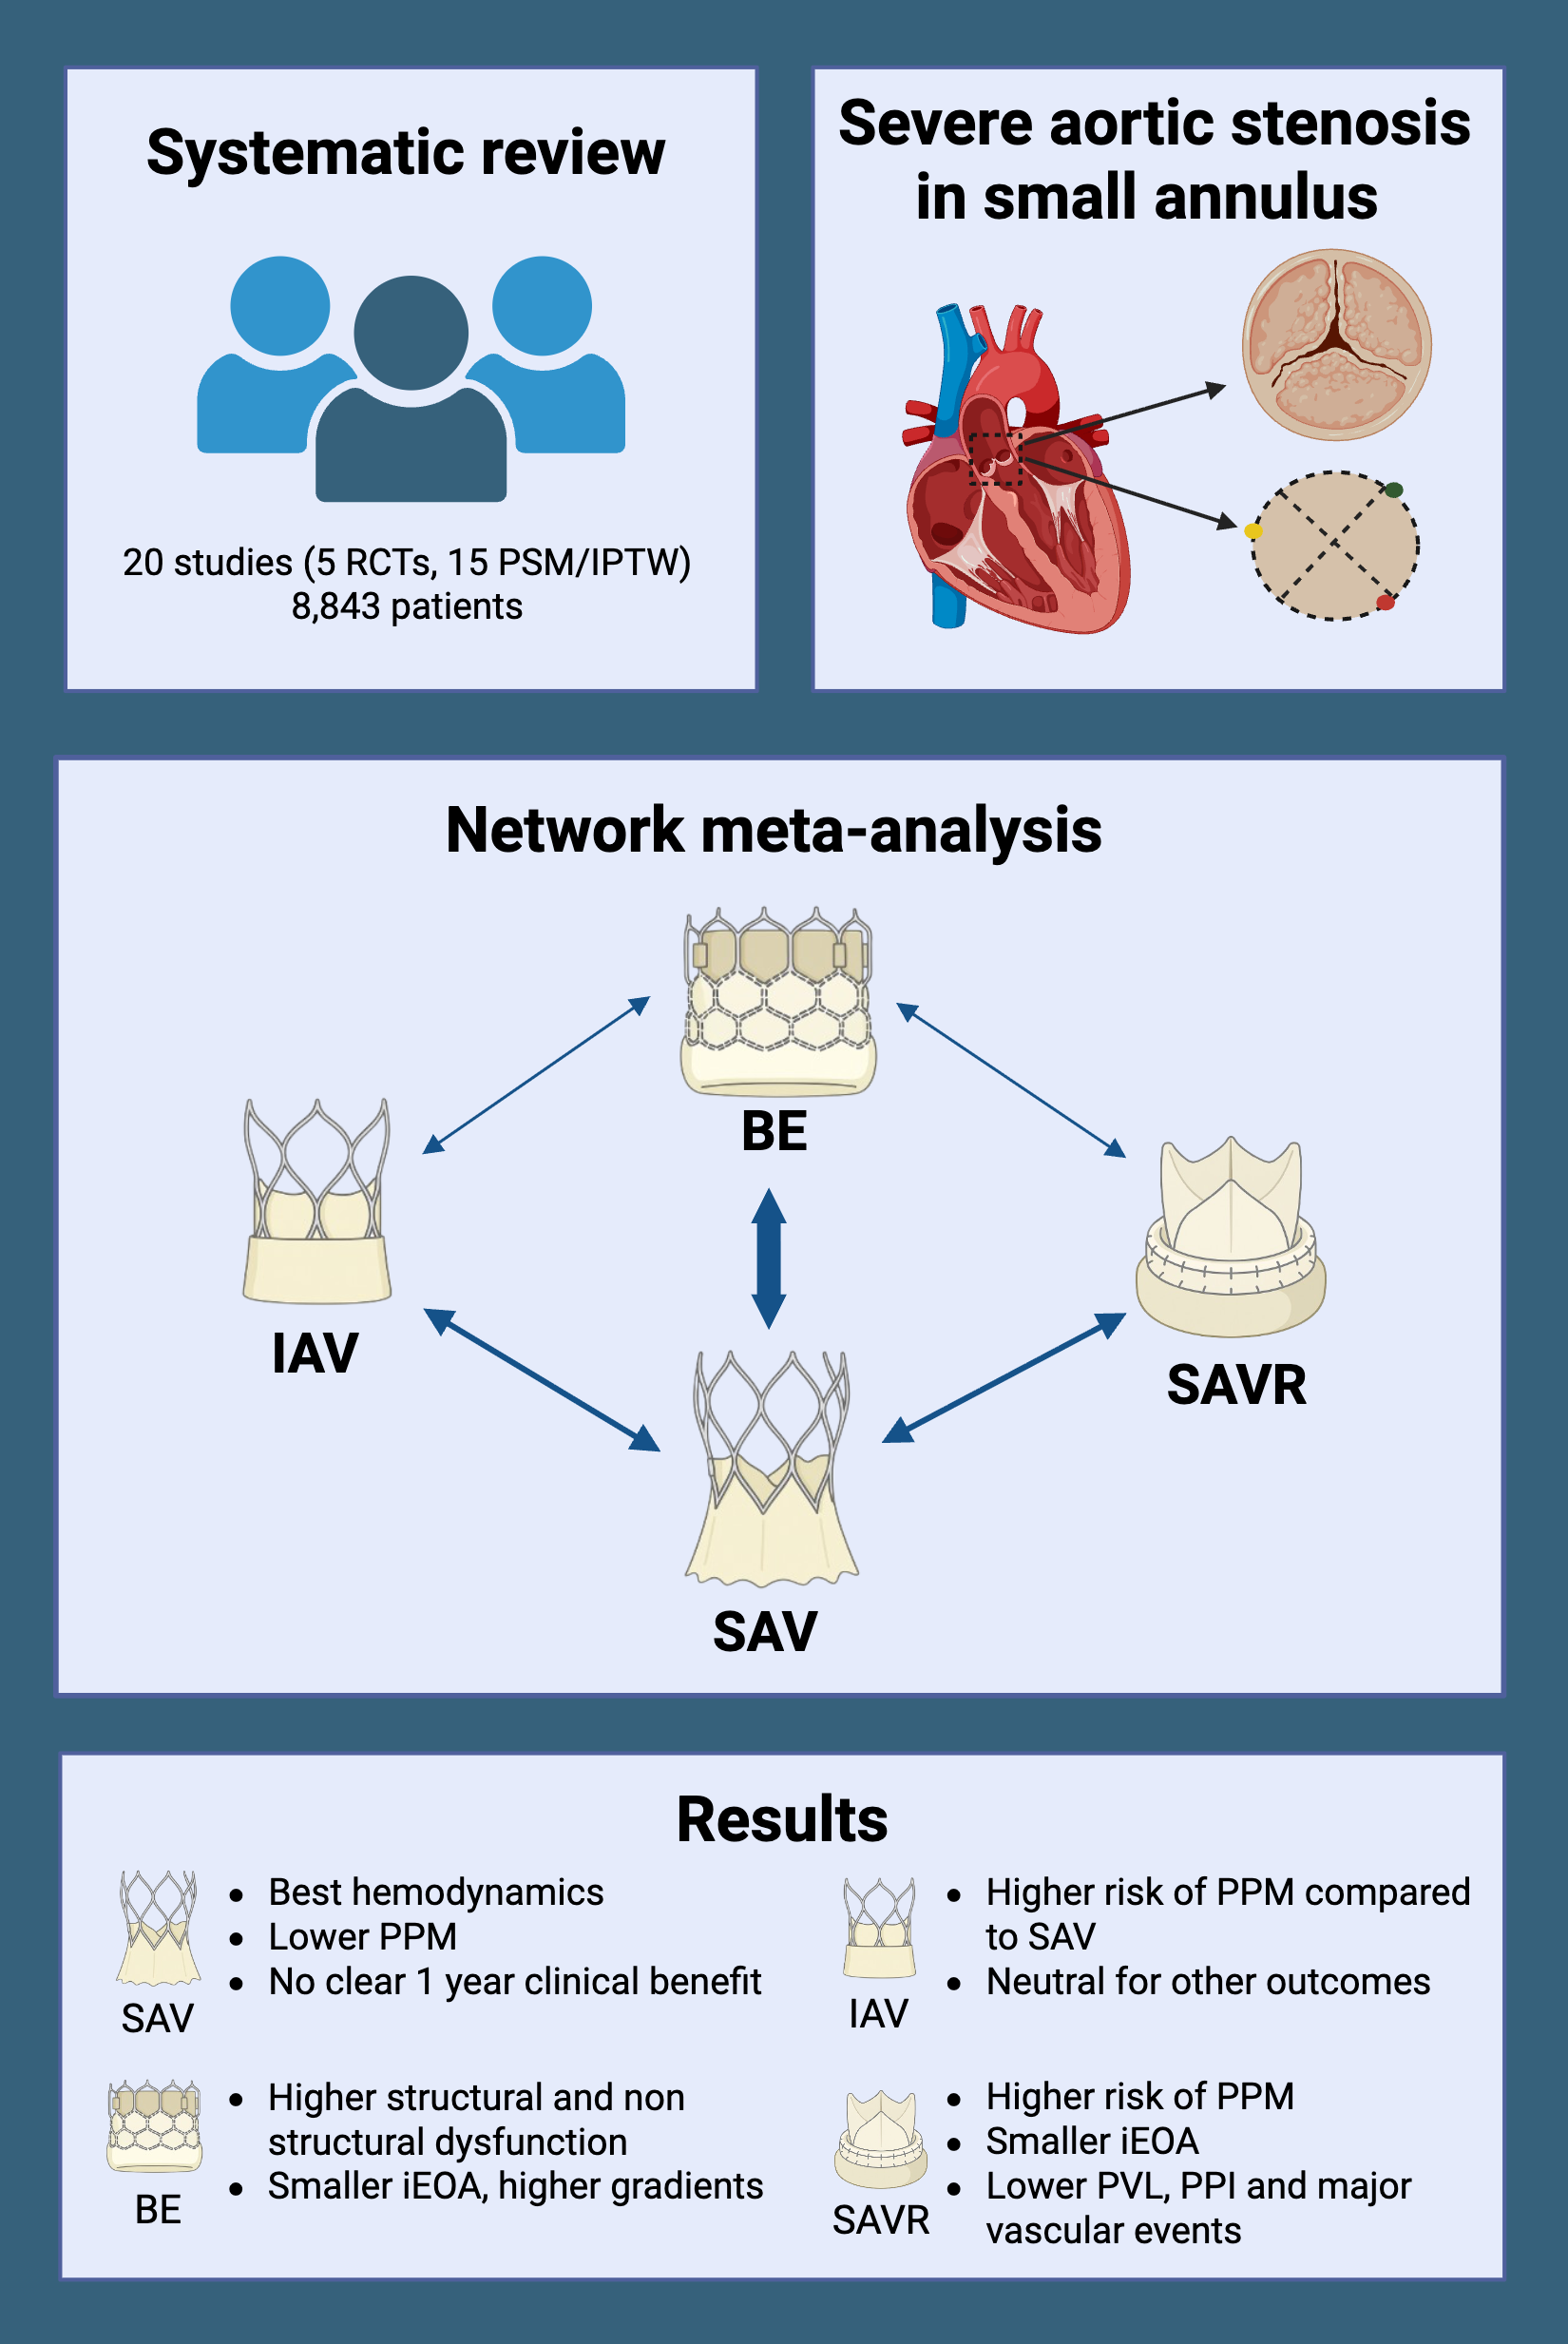
Results. Compared with supra-annular self-expanding valves (SAV), intra-annular devices and surgical aortic valve replacement (SAVR) were associated with higher risks of severe PPM (P < .05) without differences in 1-year mortality (P > .05). Balloon-expandable valves were associated with increased hemodynamic structural dysfunction (risk ratio [RR], 4.44; 95% CI, 2.08-9.45), smaller iEOA (mean difference [MD], −0.18 cm²/m²; 95% CI, −0.24 - −0.11), and higher gradients (MD 4.72 mm Hg; 95% CI, 3.52-5.92). SAVR showed the worst hemodynamics, but lower risk of paravalvular leak (RR, 0.12; 95% CI; 0.03-0.54), pacemaker implantation (RR, 0.43; 95% CI; 0.20-0.94) and major vascular complications (RR, 0.20; 95% CI, 0.08-0.47). Stroke, major bleeding, and heart failure hospitalization events were similar among groups.
Conclusions: In patients with small annuli, SAV showed superior hemodynamic profile and the lowest risk of dysfunction. These differences did not translate into a lower incidence of hard clinical outcomes at 1-year follow-up.
Introduction
Aortic stenosis (AS) with a small aortic annulus, defined as 23 mm or less by surgical prosthesis size or a valve area of less than 400 to 430 mm2 by computed tomography (CT), occurs in up to 40% of patients undergoing valve replacement and represents a critical determinant of valve hemodynamics, durability, and clinical outcomes.1-4 Small annular dimensions pose constraints on surgical prosthesis size and predispose to prosthesis-patient mismatch (PPM), a non-structural bioprosthetic valve dysfunction associated with higher residual gradients, accelerated structural valve deterioration, and increased mortality.5,6
Surgical strategies like concomitant aortic root enlargement to allow implantation of larger prostheses and the use of sutureless valves to maximize the effective orifice area have been introduced to address these challenges.7,8 These approaches, however, are technically demanding, increase procedural complexity, may be associated with higher perioperative risk, and have not demonstrated a clinical benefit in survival, limiting their general applicability.9 In parallel, transcatheter aortic valve replacement (TAVR) has gained widespread adoption in small annuli anatomies, as the absence of a sewing ring and the availability of supra-annular prostheses may translate into larger effective orifice areas and more favorable hemodynamics.1-3,10,11 Early randomized data support these hypotheses; in the VIVA (Transcatheter Aortic Valve Replacement Versus Surgical Aortic Valve Replacement for Treating Elderly Patients With Severe Aortic Stenosis and Small Aortic Annuli) trial, outcomes after TAVR and surgical aortic valve replacement (SAVR) were similar at 60 days, but the incidence of severe PPM was nearly doubled in the surgical arm.10 Similarly, the SMART (Small Annuli Randomized to Evolut or SAPIEN) trial showed superior hemodynamic performance with self-expanding supra-annular valves (SAV) compared with balloon-expandable valves (BE), without an excess of short-term clinical events.11 However, these studies were underpowered to detect differences in long-term clinical outcomes, and critical questions remain unanswered regarding the durability of different prostheses, the factors associated with bioprosthetic valve dysfunction, and the relationship between hemodynamic performance and patient-reported outcomes.
The aim of this systematic review and network meta-analysis was to evaluate surgical and transcatheter strategies in patients with small aortic annuli.
Methods
This study follows the recommendation of the PRISMA-NMA (Preferred Reporting Items for Systematic Reviews and Meta-analyses—Network Meta-Analysis) (Supplemental Table 1). The protocol was registered in the PROSPERO International Prospective Register of Systematic Reviews (CRD420251126260). Because of the nature of the study, institutional review board approval was waived.
Eligibility criteria
Studies could be included if the following criteria were satisfied: (1) patients with severe AS and a small aortic annulus undergoing surgical or transcatheter aortic valve intervention; (2) randomized design or non-randomized studies with propensity score-matched (PSM) or inverse probability treatment weighting (IPTW) adjustment; (3) comparison of at least 2 different therapeutical strategies in terms of surgical or transcatheter approach or different transcatheter heart valves (that included SAV, BE, intra-annular self-expanding devices [IAV], and SAVR); and (4) report of at least 1 pre-specified outcome of interest (structural and non-structural valve dysfunction as well as clinical endpoints). No language restrictions were applied.
Search, data extraction and qualitative assessment
Three electronic databases were screened (PubMed via MEDLINE [National Institutes of Health], Embase [Elsevier], Cochrane Central Register of Controlled Trials [Wiley]) from their inception to August 10, 2025. The full search strategy is available in Supplemental Table 2.
Three independent reviewers (J.G.C., M.L., E.E.) performed title, abstract, and full-text screening to confirm compliance with the eligibility criteria. Discordant results were solved by consensus. Key study-level and arm-level data were extracted into dedicated electronic spreadsheets and summarized. Before running the statistical analyses, 2 reviewers (M.L, E.E.) independently assessed the quality of each study by using the Cochrane’s Risk of Bias (RoB) 2 tool for randomized controlled trials (RCTs), and the Risk Of Bias In Non-randomized Studies of Interventions (ROBINS-I) tool for non-randomized studies.12,13 Disagreements were solved by consensus. The Grading of Recommendations, Assessment, Development, and Evaluations (GRADE) framework was applied to evaluate the certainty of evidence for each prespecified outcome according to the following PICO question: In patients with severe AS and a small annulus (Population), does SAV-TAVR (Intervention), compared with intra-annular, BE, or SAVR (Comparators), result in differences in hemodynamic performance or clinical outcomes (Outcomes)?
Endpoints
The prespecified primary outcomes included severe PPM and all-cause mortality. Secondary outcomes of interest included the following:
- Hemodynamic structural valve dysfunction during follow-up, defined as a mean aortic valve gradient of 20 mm Hg or higher, with a concomitant decrease in effective orifice area (EOA) (≥0.3 cm2 or ≥25%) and/or decrease in Doppler velocity index (≥0.1 or ≥20%)14
- Non-structural valve dysfunction endpoints during follow-up (moderate PPM and at least moderate paravalvular leak [PVL]),
- Postprocedural hemodynamics (including indexed EOA [iEOA] and transvalvular mean pressure gradient),
- Clinical outcomes, such as stroke, major bleeding, major vascular complications, permanent pacemaker implantation (PPI), hospitalization for heart failure (HF), and valve reintervention.
All endpoints were study-defined but followed the Valve Academic Research Consortium (VARC) criteria iterations.15-18 The detailed definitions are shown in Supplemental Table 3.
Statistical analysis
Categorical variables are reported as counts and proportions and continuous variables as means or medians. The analyses were conducted in a frequentist random-effects network meta-analysis framework. Comparison between the valve designs were reported as mean differences (MDs) for continuous and risk ratios (RRs) for binary outcomes, respectively, along with 95% confidence intervals (CIs). The results are displayed by using relative effect tables and forest plots. Each treatment was ranked according to surface under the cumulative ranking curve (SUCRA) values. Inconsistency was explored through node-splitting analysis and Higgins ì global consistency test.19 Statistical heterogeneity was assessed through τ2 and I2 and categorized as low, moderate, or high for I2 levels of less than 25%, 25% to 50% and greater than 50%, respectively.
Sensitivity analyses were conducted by considering only randomized controlled trials, using a standardized definition of less than 430 mm², using exclusively the VARC-3 outcome definition; and excluding patients at high risk and those treated with earlier-generation valve prostheses. Meta-regression analyses were used to explore the influence of female sex, age, and surgical risk on the outcomes of interest. In order to assess whether the effect of valve type in the rate of PPM (either moderate and severe PPM) was driven by differences in aortic valve area (AVA) or by differences in body surface area (BSA), a random- effects meta-regression model was fitted by restricted maximum likelihood (REML). The impact of small-study effects and publication bias was assessed by comparison-adjusted funnel plots complemented by the Egger’s test. All analyses were performed through R 4.4.2 (R Project for Statistical Computing).
Results
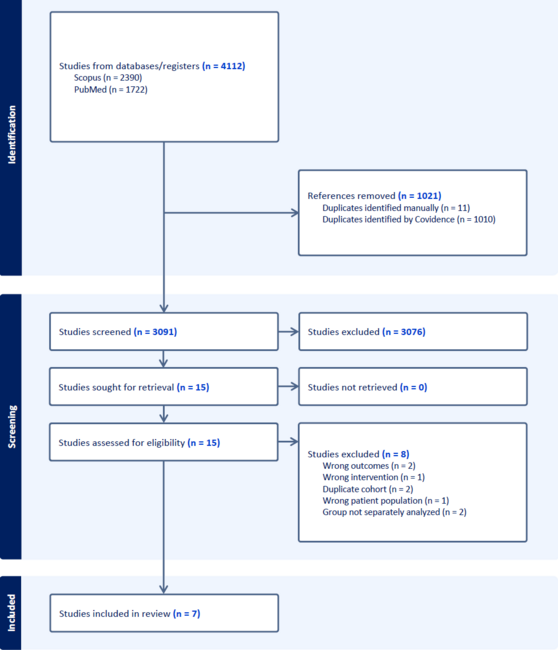
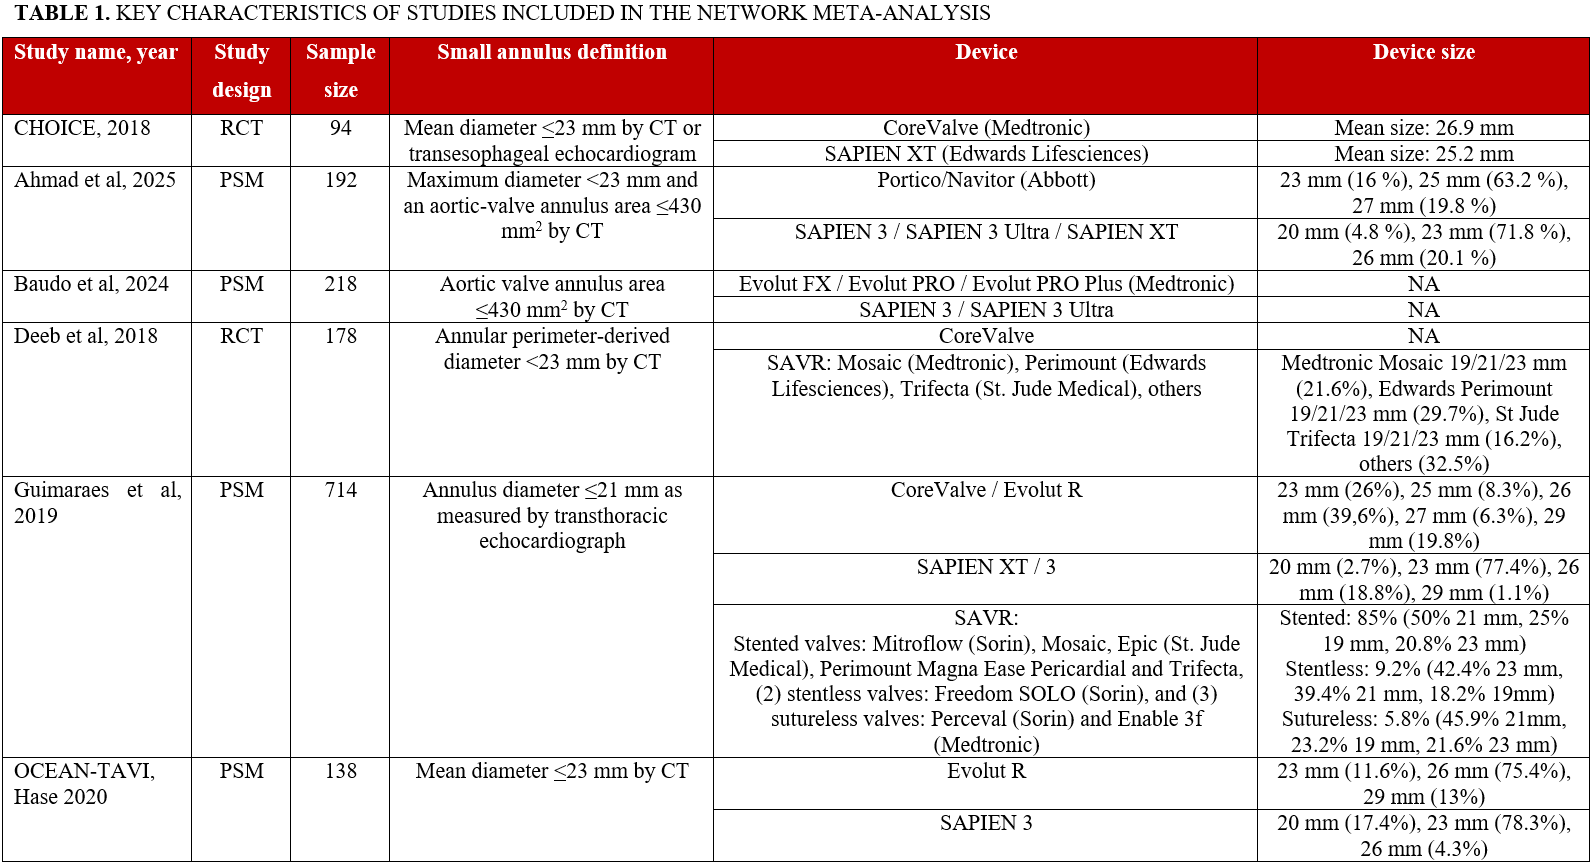
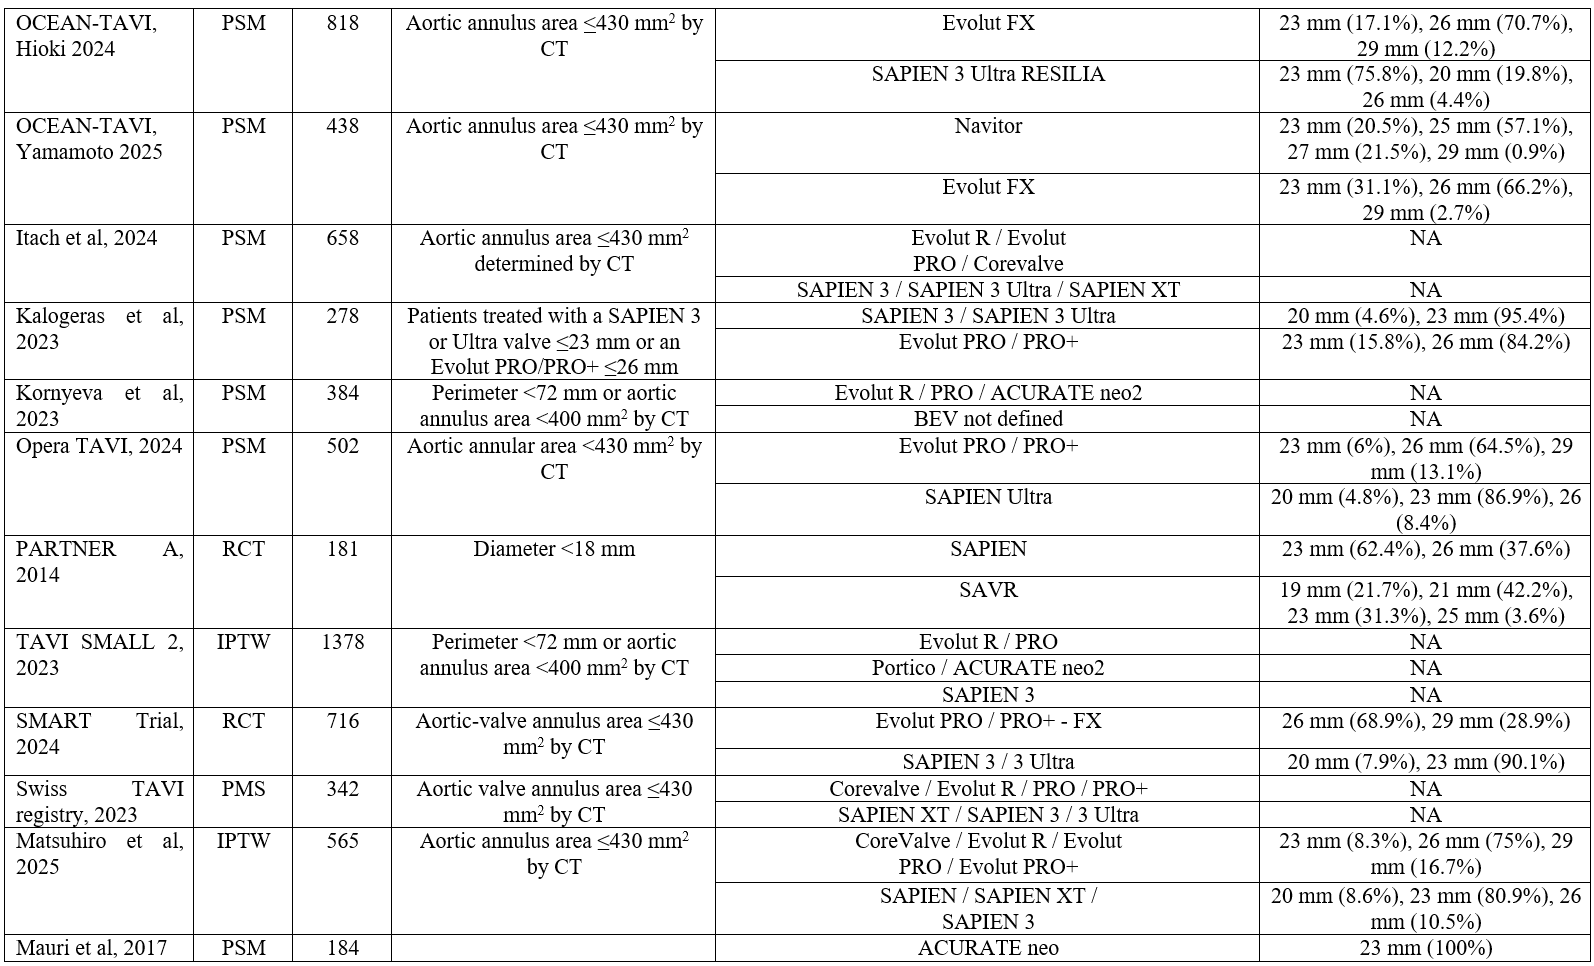
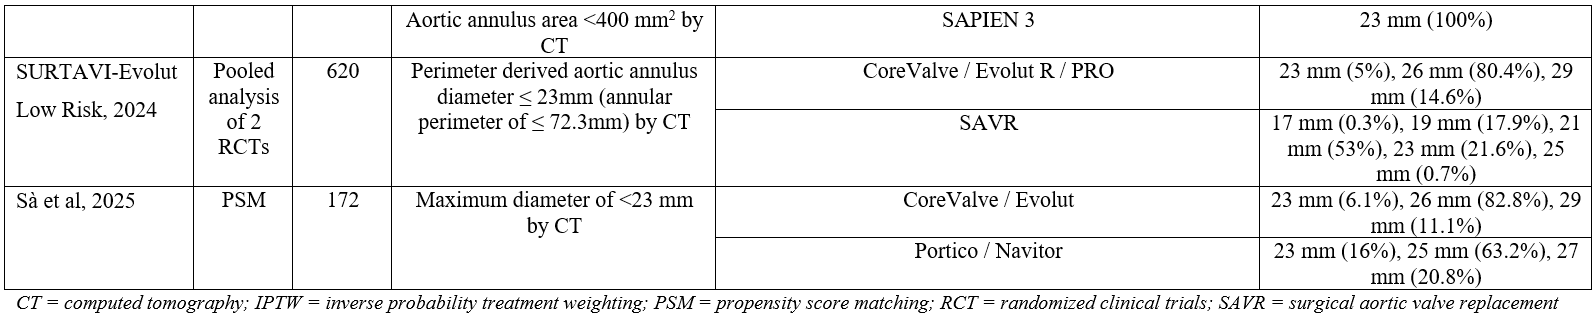
Following the screening phase, a total of 20 studies comprising 8843 patients were included, with a mean weighted follow-up of 1.4 years, 7782 (88%) of which had a follow-up of 1 year (Figure 1).20-39 The full study selection process is summarized in Supplemental Figure 1. Key characteristics of the included studies are reported in Table 1. Demographic and procedural characteristics were consistent across included studies (Table 2).
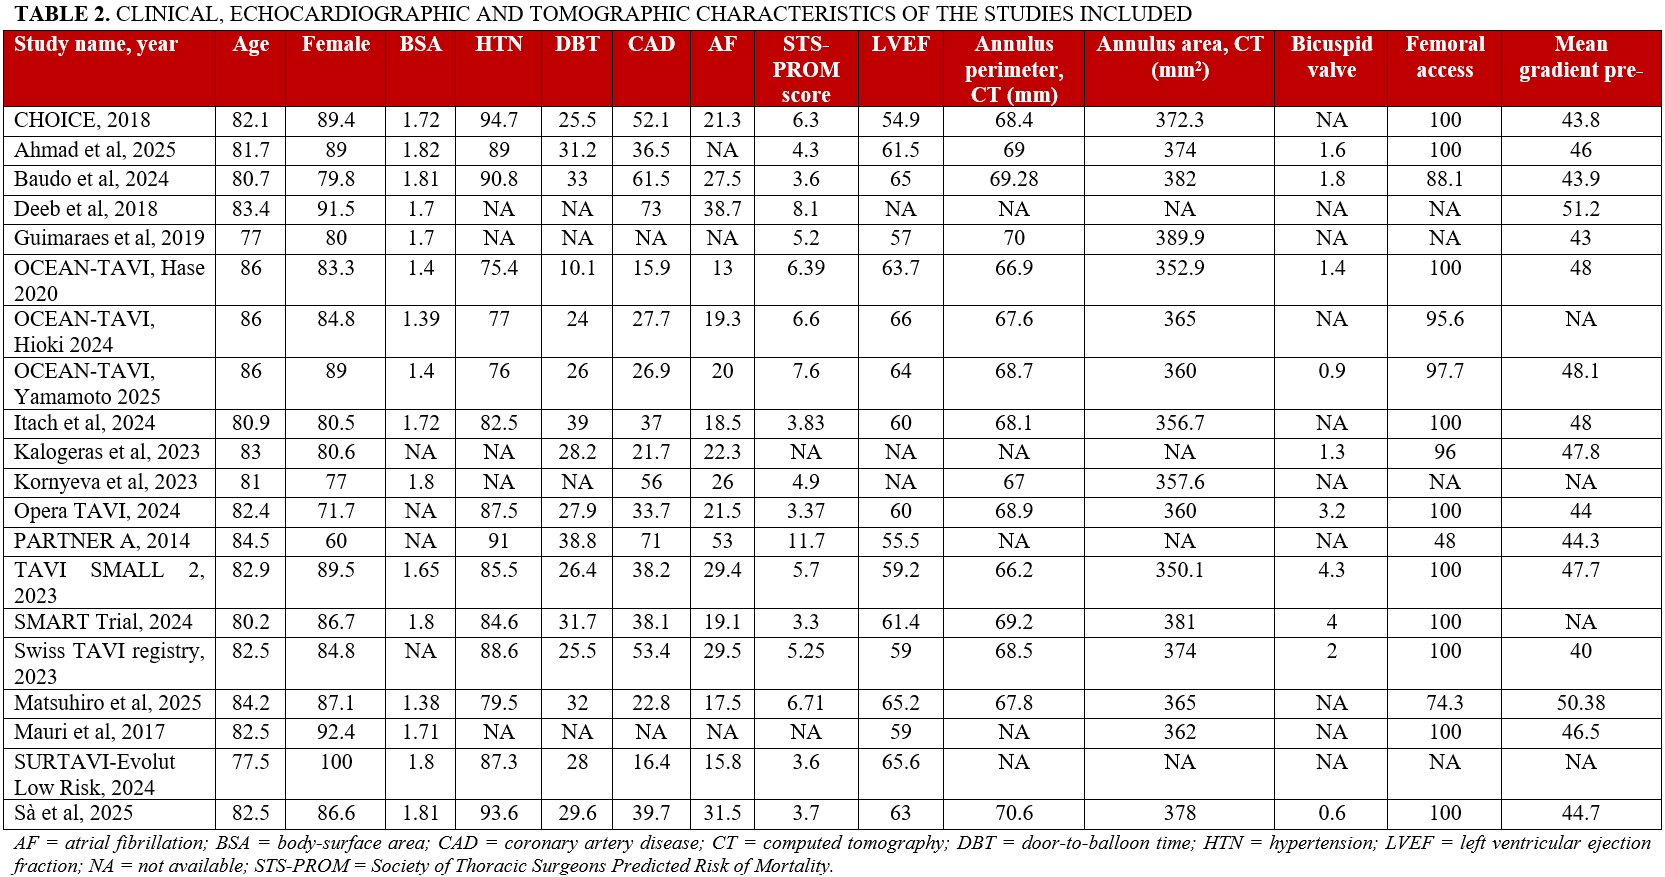
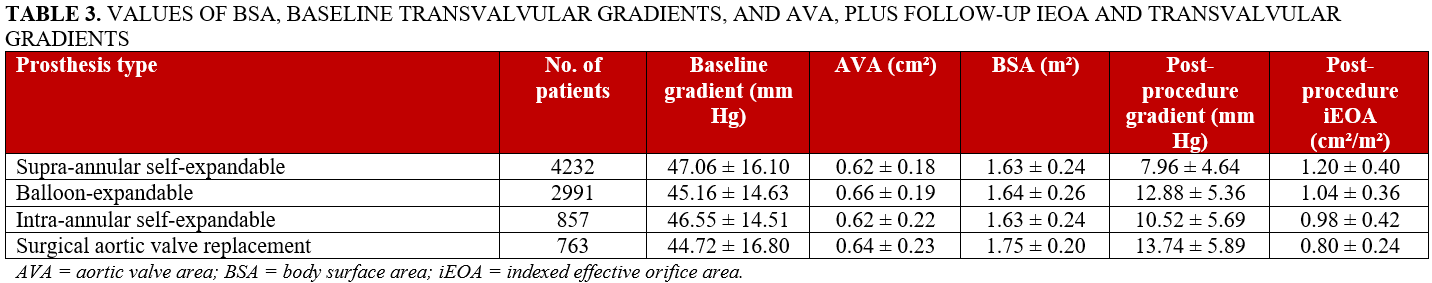
Overall, no studies were deemed at high risk for bias (Supplemental Figures 2 and 3, Supplemental Table 4), while no sign of publication bias was detected (Supplemental Figure 4). The weighted mean age was 82 years (interquartile range [IQR] 77-86), with 7430 (84% (60%-100%)) of patients were women. Bicuspid aortic valve anatomy was uncommon (~0.6%-4.3%). Traditional cardiovascular risk factors were highly prevalent (hypertension ~75%-95% and diabetes mellitus ~10%-39%). Reported Society of Thoracic Surgeons Predicted Risk of Mortality (STS-PROM) values ranged from 3% to 12%, and the left ventricular ejection fraction (LVEF) was largely preserved (~55%-69%). At CT evaluation, the annular perimeter measured approximately 66 to 70 mm, while the annular area was approximately 350 to 390 mm². Transfemoral access predominated in contemporary series (generally ≥95%), although early-era studies reported lower rates. The nominal values of BSA, baseline transvalvular gradients, and AVA, as well as the follow-up iEAO and transvalvular gradients, are presented in Table 3.
Primary endpoint
Compared with SAV, all intra-annular devices had an increased risk of severe PPM at 1 year of follow-up ([BE: RR, 2.64; 95% CI, 1.91-3.65; P < .001], [IAV: RR, 1.89; 95% CI, 1.15-3.11; P = .001] and [SAVR: RR, 3.23; 95% CI, 2.07-5.03; P < .001]). On the other hand, there were no differences in all-cause mortality among the devices (all P > .05) (Figure 2, Supplemental Table 5). Although heterogeneity was low (I2 = 23%, τ2 = 0.065), node-splitting analysis revealed inconsistency between direct and indirect comparisons, which was improved with the one-out analysis (Supplemental Table 6). The SUCRA analysis ranked the SAV group first in terms of severe PPM events and all-cause death.
Structural and nonstructural valve dysfunction, and postprocedural hemodynamics
Compared with SAV, all intra-annular devices had an increased risk of moderate PPM ([BE: RR, 2.36; 95% CI, 1.62-3.45; P < .0001], [IAV: RR, 2.16; 95% CI, 1.12-4.17; P = .021], and [SAVR: RR, 2.37; 95% CI, 1.18-4.76; P = .001]). SAVR was associated with a lower risk of PVL (RR, 0.12; 95% CI, 0.03-0.54; P = .005). There were no differences among TAVR prostheses regarding PVL (all P > .05) (Figure 2). Heterogeneity was deemed moderate (I2 = 42.6%, τ2 = 0.441). The SUCRA analysis ranked the SAV group first in terms of moderate PPM events, but SAVR first in terms of PVL events.
Compared with SAV, BEs were associated with lower iEOA (MD −0.18; 95% CI, −0.24 - −0.11; P < .0001), higher mean gradient (MD 4.72 mm Hg; 95% CI, 3.52-5.92; P < .001) and higher risk of hemodynamic dysfunction (RR, 4.44; 95% CI, 2.08-9.45; P = .001) (Figure 3). IAV showed no significant difference in iEOA, mean gradients, or hemodynamic structural valve dysfunction compared with SAV (all P > .05). SAVR also showed lower iEOA (MD −0.26 cm²/m²; 95% CI, −0.37 - −0.16]; P < .0001) and higher mean gradients (MD 5.85 mm Hg; 95% CI, 3.65-8.04; P < .0001), but no differences in hemodynamic structural valve dysfunction (RR, 4.35; 95% CI, 0.86-21.89; P = .074) (Figure 3). The overall heterogeneity was deemed high for these outcomes (I2 = 71.6%, τ2 = 0.009). SAV showed the highest probability of ranking among the valve designs.
Node-splitting analysis revealed inconsistency between direct and indirect comparisons within moderate PPM, and iEOA and transvalvular gradients, all of which were resolved with the one-out analysis (Supplemental Table 6).

Clinical endpoints
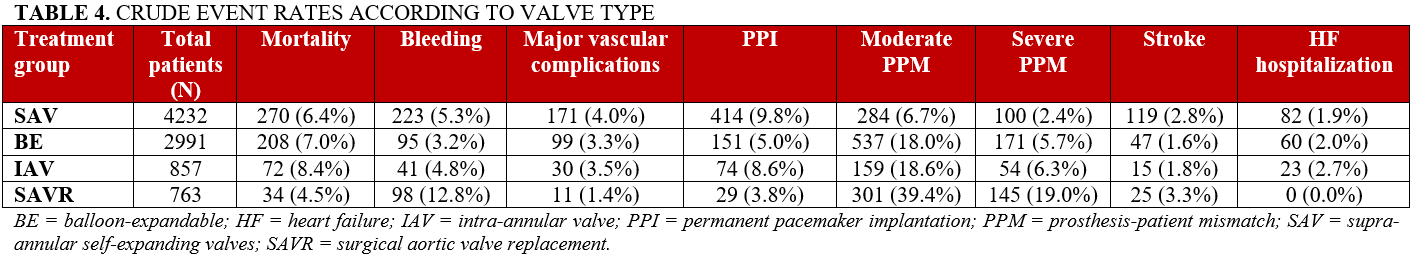
Compared to SAV, BE and IAV did not show statistical differences in terms of major bleeding, major vascular events, permanent pacemaker implantation (PPI), stroke, HF hospitalizations, or valve reinterventions (Figure 4). SAVR was associated with lower risk of major vascular events (RR, 0.20; 95% CI, 0.08-0.47; P < .001) and PPI (RR, 0.43; 95% CI, 0.20-0.94; P = .035) compared with SAV, without differences in terms of major bleeding, stroke, or valve re-interventions. The heterogeneity in major bleeding (I2 = 51%, τ2 = 0.115) and PPI (I2 = 67.5%, τ2 = 0.213) was deemed high, moderate in stroke, and low in the rest of the events. Significant inconsistency was detected for major bleeding and stroke, which was resolved with the one-out analysis (P < .05) (Supplemental Table 6). Figure 5 shows the different valve design rankings with SUCRA analysis in all endpoints. Crude events according to valve type are presented in Table 4.
Sensitivity analyses
When performing only RCTs sub-analysis, SAV was associated with a lower risk of heart, stroke, and vascular disease (HSVD) compared with SAVR (RR, 0.31; 95% CI, 0.13-0.72; P < .05); meanwhile, SAVR continued to show superiority in terms of major vascular events and PPI compared with the percutaneous devices (all P < .05), with a reduced heterogeneity of the model (Supplemental Table 7). The sensitivity analysis restricted to patients with a standardized definition of small annulus (<430 mm²) confirmed that BE showed a worse performance compared with SAV valves in terms of both moderate (RR, 2.00; 95% CI, 1.43-2.80; P < .001) and severe PPM (RR, 2.47; 95% CI, 1.75-3.49; P < .001). In contrast, SAVR did not demonstrate statistically significant advantages in terms of PVL or major vascular complications (both P > .05). Notably, both BE and SAVR were associated with significantly lower rates of PPI compared with SAV (BE: RR, 0.65; 95% CI, 0.45-0.92; P = .01] and SAVR [RR, 0.30; 95% CI, 0.13-0.68; P = .004]) (Supplemental Table 8).
In the sensitivity analysis removing the studies that included high-risk patients treated with first-generation devices, the previously observed advantage of SAVR over SAV in terms of PVL was no longer statistically significant, though it retained superiority in terms of major vascular events (Supplemental Table 9). In the sensitivity analysis including only the studies that reported the outcomes with the VARC-3 analysis, SAV continued to demonstrate superiority to the rest of intra-annular devices in terms of severe and moderate PPM, and was comparable to BE and SAVR in terms of HSVD, showing similarity regarding all-cause death.
Regarding PVL, SAVR and BE exhibited lower rates of PVL events relative to SAV. Overall, clinical endpoints in the sensitivity analysis mirrored those of the main analysis, supporting the robustness of the primary findings (Supplemental Table 10). In the meta-regression of the comparison between self-expandable and BE, female sex was associated with lower mean transvalvular gradients after TAVR (β = –0.076, P = .047). In the model adjusted for the inference of valve type and AVA and BSA in moderate and severe PPM events, SAV retained significantly lower risk of both moderate and severe PPM relative to BE (P = .003 and P < .0001), as well as lower risk of severe PPM relative to SAVR (P = .021) (Supplemental Tables 11 and 12).
Discussion
The main results of our network meta-analysis can be summarized as follows: SAV showed superior hemodynamic performance compared with intra-annular devices and SAVR in terms of severe PPM, but without an impact on all-cause death. Although SAVR ranked worst of most hemodynamic endpoints, it showed lower risk of PVL, PPI, and major vascular complications—advantages that were attenuated in sensitivity analyses restricted to patients with a standardized small annulus definition or after excluding high-risk patients treated with first-generation devices. However, these differences did not translate into a higher incidence of clinical outcomes at 1 year of follow-up (Figure 4). Although previous meta-analyses have yielded evidence regarding the comparison between BE and supra-annular TAVR prosthesis or with the comparison with SAVR, the network meta-analysis framework allows the combination of evidence from both direct and indirect comparisons between different supra- and intra-annular design, providing further insights in the topic.40-42
Patients with a small aortic annulus face multiple procedural challenges for both TAVR and SAVR, including a higher risk of PPM and annulus rupture.43 Elevated transprosthetic pressure gradients, especially when adjusted by flow, increase LV wall stress and workload, leading to maladaptive remodeling such as LV hypertrophy and diastolic dysfunction. Over time, this additional stress can result in HF symptoms, reduced exercise tolerance, and poor clinical outcomes, and is associated with an increased risk of events.44,45 Moreover, severe PPM has been linked to a 25% increased risk of mortality and no reversal of LV remodeling after TAVR and SAVR.6,46,47 Given the high prevalence of small annulus anatomy (up to 35 % in patients undergoing SAVR and up to 20% of patients undergoing TAVR), recognizing these risks and considering alternative strategies to minimize complications is essential.48
In our study, the superiority of SAV valves in terms of predischarge hemodynamics compared with intra-annular designs (either IAV, BE, or SAVR) is likely explained by structural features. As the leaflets are mounted above the native annulus, the leaflet-free edges are able to open in a larger geometric orifice than the annular diameter itself. Also, the flared inflow and outflow reduce the degree of flow acceleration through the valve. This translated into better iEOA, lower transvalvular gradients, and lower rates of moderate-to-severe PPM in the SAV group. These findings align with the SMART trial, where self-expanding valves outperformed BE in terms of mean gradient, EOA, structural valve dysfunction, and PPM at 30 days.26 Interestingly, sensitivity analysis excluding high-risk cohorts and early-generation devices attenuated these differences—possibly reflecting the improved performance of newer BE designs, such as the SAPIEN 3 Ultra RESILIA (Edwards Lifesciences), which features a modified leaflet-sewing technique. Hioki et al reported that SAPIEN 3 Ultra RESILIA had lower rates of severe PPM and a mean gradient of greater than 20 mm Hg compared with SAPIEN 3, though rates remained higher than with the Evolut FX (Medtronic).27
The hemodynamic advantage of SAV extends to comparisons with SAVR, as demonstrated in subgroup analyses of the SURTAVI and CoreValve High-Risk trials, both of which reported superior transvalvular hemodynamics and a lower incidence of PPM compared with surgery.23,24 An observation warranting further investigation is that, although the comparison between SAV and IAV revealed no differences in iEOA or transvalvular mean gradient, the network meta-analysis—combining direct and indirect comparisons—showed that IAV were associated with a higher risk of moderate and severe PPM, with no evidence of inconsistency between direct and indirect estimates. This finding contrasts with the results of the OCEAN-TAVI registry reported by Yamamoto et al, in which no significant differences were observed in the incidence of severe PPM.39
However, these hemodynamic advantages did not translate into clinical benefits at the 1-year follow-up, as no differences were observed in all-cause mortality, stroke, HF hospitalizations, or major bleeding. Indeed, the prognostic significance of PPM following TAVR remains a matter of debate, with some studies demonstrating a significant association with adverse outcomes, whereas others failed to confirm this relationship.46,49,50 Certain subgroups, however, may be at increased risk of severe PPM, such as patients with reduced LVEF.51 Owing to the limited granularity of the data reported across the included studies, a sensitivity analysis addressing this subgroup could not be performed. Moreover, after excluding earlier studies that compared first-generation valves in high-risk patients, the previously noted advantages of SAVR—particularly regarding PPI and PVL—were no longer statistically significant. Indeed, the fact that the advantage of SAVR over transcatheter devices in terms of PVL was attenuated after excluding high-risk, early-generation-device studies raises the possibility that this finding reflects, at least in part, patient selection and procedural era rather than a specific benefit of the surgical approach itself.
Several factors may explain these findings. First, the short follow-up of patients may not be sufficient in order to capture the onset of clinical events, thus potentially masking the negative long-term clinical impact of PPM. Second, some studies used the VARC-2 criteria, introducing variability into outcome definition.28,29,33 Lastly, all PPM analyses in our study were based on measured rather than predicted PPM. Measured PPM is derived from the patient’s EOA obtained by echocardiography, whereas predicted PPM is more specific to the intrinsic hemodynamic performance of the prosthetic valve and is not influenced by patient flow status or by measurement variability and error.52 In an international multicenter study, the prevalence of severe PPM was higher when using the measured method; however, its negative impact was no longer evident after adjustment for confounding factors.53 Moreover, a recent study showed that invasive gradients, but not echocardiographic measure gradients, were correlated with a higher risk for all-cause mortality at 30 days, 1 year, and 2 years.54
Finally, an interesting feature of our cohort is the relatively high proportion of women, a population often underrepresented in TAVR studies. This is consistent with the known higher prevalence of small aortic annulus in women, who also tend to have smaller LV outflow tract dimensions despite similar aortic root anatomy—a factor that may influence both procedural strategy and outcomes.55 Indeed, the meta-regression analysis showed that women had better hemodynamics after TAVR, findings that may explain the superiority of TAVR (with SAPIEN 3 or SAPIEN 3 Ultra) vs SAVR in female patients, driven primarily by fewer rehospitalization events in the TAVR group.56 Our results are in line with these results, as the meta-regression revealed that female sex was associated with lower mean transvalvular gradients after TAVR. Furthermore, although BSA was a significant predictor of either moderate or severe PPM (consistent with the mathematical dependence of the iEOA denominator on BSA), SAV was consistently associated with the lowest rate of PPM, both moderate and severe, among the 4 prosthesis types evaluated, even after adjustment for AVA and BSA in the meta-regression model.
Limitations
First, the definitions of small annulus were different among some studies included. Nevertheless, we performed a sensitivity analysis that confirmed the worse performance of BE in terms of moderate and severe PPM, whereas SAVR lost its benefit in terms of PPI and PVL. Second, as outcomes were assessed at 1 year, clinical events that typically occur over longer follow-up periods may be underestimated because of follow-up bias. Third, some included studies employed PSM or IPTW, which—while useful in reducing selection and treatment biases—does not account for all baseline differences between groups and, therefore, may not ensure a perfectly balanced comparison. Their inclusion likely contributed to the high degree of heterogeneity observed for some of the endpoints of interest; however, a sensitivity analysis restricted to RCTs substantially reduced heterogeneity while confirming the robustness of the findings. Moreover, the inclusion of non-randomized clinical trials increased inconsistency in the clinical and hemodynamic outcomes within the network structure, though this inconsistency was resolved through a leave-one-out analysis. Fourth, not all studies provided an echocardiography core lab, potentially influencing the reported incidence of PPM, especially in states of low flow which may lead to pseudo-severe PPM, and influencing outcomes. In addition, patients with greater annular calcification and more challenging anatomy were likely preferentially treated with BE, thereby potentially disadvantaging BEs in outcome comparisons. Finally, other relevant factors that could affect the results—such as the prevalence of valve under- or oversizing and the amount or distribution of annular calcification—could not be evaluated.
Conclusions
In patients with severe aortic stenosis and a small annulus, SAV showed superior hemodynamic performance vs IAV, BE, and surgical aortic valves in terms of predischarge hemodynamics and short-term structural and non-structural valve dysfunction. No differences were observed in most clinical outcomes, except for the superiority of SAVR in reducing major vascular events, PPI, and PVL—advantages that were attenuated in sensitivity analyses restricted to patients with a standardized small annulus definition or after excluding high-risk patients treated with first-generation devices.
Affiliations and Disclosures
Juan Guido Chiabrando, MD, MSc1; Marco Lombardi, MD2,3; Edoardo Elia, MD2; Claudio Laudani, MD, MSc4,5; Giovanni Occhipinti, MD6,7; Ander Regueiro, MD6,7; Andrea Audo, MD8; Giulia Maj, MD9; Carlos Giuliani, MD10; Salvatore Garibaldi, MD1; Josep Rodés-Cabau, MD, PhD10; Philippe Pibarot, DVM, PhD10; Rocco Vergallo, MD, PhD3,11; Italo Porto, MD, PhD3,11; Nicolas M. Van Mieghem, MD, PhD12; Giuseppe Patti, MD, PhD13,14; Gioel Gabrio Secco, MD, PhD2,14
Dr Chiabrando and Dr Lombardi contributed equally.
From the 1Interventional Cardiology Unit, UOSD Emodinamica, Ospedale Barone Romeo, Patti, Italy; 2Interventional Cardiology Unit, AOU SS Antonio e Biagio e Cesare Arrigo, Alessandria, Italy; 3Department of Internal Medicine and Medical Specialties (DIMI), Università di Genova, Genova, Italy; 4Division of Cardiology, Azienda Ospedaliero-Universitaria Policlinico "Rodolico – San Marco", University of Catania, Catania, Italy; 5Division of Cardiology, University of Florida College of Medicine-Jacksonville, Jacksonville, Florida; 6Institut Clinic Cardiovascular, Hospital Clínic de Barcelona, University of Barcelona, Barcelona, Spain; 7Instituto de Investigaciones Biomédicas Agusti Pi i Sunyer (IDIBAPS), Barcelona, Spain; 8Division of Cardiac Surgery, AOU SS, Antonio e Biagio e Cesare Arrigo, Alessandria, Italy; 9Division of Cardiothoracic Intensive Care, AOU SS, Antonio e Biagio e Cesare Arrigo, Alessandria, Italy; 10Institut Universitaire de Cardiologie et de Pneumologie de Québec, Université Laval, Quebec City, Quebec, Canada; 11Cardiothoracic and Vascular Department (DICATOV), IRCCS Ospedale Policlinico San Martino, Genova, Italy; 12Department of Cardiology, Thoraxcenter, Erasmus University Medical Center, Rotterdam, the Netherlands; 13Division of Cardiology, Maggiore della Carità Hospital, Novara, Italy; 14Department of Translational Medicine, University of Eastern Piedmont, Novara, Italy.
Disclosures: Dr Lombardi reports consultancy for Boston Scientific and speaker fees for Philips. Dr Van Mieghem has received research grants from Abbott, Boston Scientific, Medtronic, Meril, Pie Medical Imaging, PulseCath BV, and Teleflex; and is consultant for Abbott, Abiomed, Adjust Medical SA, Alleviant Medical, Inc., AnchorValve, Anteris, Approxima Srl, Boston Scientific, Daiichi Sankyo, Haemonetics, LUMA Vision, Materialise, Medtronic, PercAssist, Pie Medical Imaging, Polares Medical, PulseCath BV, Secure Closure, Supira Medical, Siemens, and Vivasure. The remaining authors report no financial relationships or conflicts of interest regarding the content herein.
Data availability statement: All meta-analytic data are available upon reasonable request to the corresponding author.
Address for correspondence: Juan Guido Chiabrando, MD, MSc, UOSD Emodinamica Patti, Italy
Via Giuseppe Mazzini, 14, Patti (ME) 98066, Italy. Email: jgchiabrando@gmail.com; X: @Jgchiabrando1; Instagram: @juangch11
References
1. Leone PP, Regazzoli D, Pagnesi M, et al; TAVI-SMALL Investigators. Predictors and clinical impact of prosthesis-patient mismatch after self-expandable TAVR in small annuli. JACC Cardiovasc Interv. 2021;14(11):1218-1228. doi:10.1016/j.jcin.2021.03.060
2. Trimaille A, Carmona A, Hmadeh S, et al. Transcatheter aortic valve durability: focus on structural valve deterioration. J Am Heart Assoc. 2025;14(13):e041505. doi:10.1161/JAHA.125.041505
3. Ternacle J, Pibarot P, Herrmann HC, et al. Prosthesis-patient mismatch after aortic valve replacement in the PARTNER 2 trial and registry. JACC Cardiovasc Interv. 2021;14(13):1466-1477. doi:10.1016/j.jcin.2021.03.069
4. Levesque T, Eltchaninoff H, Chabannes R, et al. Impact of prosthesis-patient mismatch after transcatheter aortic valve replacement. Can J Cardiol. 2024;40(1):113-122. doi:10.1016/j.cjca.2023.09.012
5. Nam L, Singh R, Hirji SA, et al. A multi-institutional study on the prevalence and clinical impact of patient-prosthesis mismatch in surgical aortic valve replacement. Ann Thorac Surg. 2025;120(3):478-486. doi:10.1016/j.athoracsur.2025.04.036
6. Suruga K, Patel V, Nagasaka T, et al. Prosthesis-patient mismatch in young and low-risk patients after newer generation balloon-expandable transcatheter aortic valve replacement. JACC Cardiovasc Interv. 2025;18(12):1512-1523. doi:10.1016/j.jcin.2025.05.003
7. Eisenga JB, Pickering T, McCullough KA, et al. Surgeon frequency of aortic root enlargement and long-term survival in Medicare beneficiaries undergoing surgical aortic valve replacement. Am J Cardiol. 2025;246:16-24. doi:10.1016/j.amjcard.2025.03.009
8. Sá MP, Jabagi H, Dokollari A, et al. Early and late outcomes of surgical aortic valve replacement with sutureless and rapid-deployment valves versus transcatheter aortic valve implantation: meta-analysis with reconstructed time-to-event data of matched studies. Catheter Cardiovasc Interv. 2022;99(6):1886-1896. doi:10.1002/ccd.30162
9. Sá MP, Van den Eynde J, Amabile A, et al. Late outcomes after aortic root enlargement during aortic valve replacement: meta-analysis with reconstructed time-to-event data. J Cardiothorac Vasc Anesth. 2022;36(8 Pt B):3065-3073. doi:10.1053/j.jvca.2022.04.013
10. Rodés-Cabau J, Ribeiro HB, Mohammadi S, et al; VIVA (Transcatheter Aortic Valve Replacement Versus Surgical Aortic Valve Replacement for Treating Elderly Patients With Severe Aortic Stenosis and Small Aortic Annuli) Trial Investigators. Transcatheter or surgical aortic valve replacement in patients with severe aortic stenosis and small aortic annulus: a randomized clinical trial. Circulation. 2024;149(9):644-655. doi:10.1161/CIRCULATIONAHA.123.067326
11. Tchétché D, Mehran R, Blackman DJ, et al. Transcatheter aortic valve implantation by valve type in women with small annuli: results from the SMART randomized clinical trial. JAMA Cardiol. 2024;9(12):1106-1114. doi:10.1001/jamacardio.2024.3241
12. Sterne JAC, Savović J, Page MJ, et al. RoB 2: a revised tool for assessing risk of bias in randomised trials. BMJ. 2019;366:l4898. doi:10.1136/bmj.l4898
13. Sterne JA, Hernán MA, Reeves BC, et al. ROBINS-I: a tool for assessing risk of bias in non-randomised studies of interventions. BMJ. 2016;355:i4919. doi:10.1136/bmj.i4919
14. Pibarot P, Herrmann HC, Wu C, et al; Heart Valve Collaboratory. Standardized definitions for bioprosthetic valve dysfunction following aortic or mitral valve replacement: JACC state-of-the-art review. J Am Coll Cardiol. 2022;80(5):545-561. doi:10.1016/j.jacc.2022.06.002
15. Head SJ, Mokhles MM, Osnabrugge RL, et al. The impact of prosthesis-patient mismatch on long-term survival after aortic valve replacement: a systematic review and meta-analysis of 34 observational studies comprising 27 186 patients with 133 141 patient-years. Eur Heart J. 2012;33(12):1518-1529. doi:10.1093/eurheartj/ehs003
16. Lee G, Chikwe J, Milojevic M, et al. ESC/EACTS vs. ACC/AHA guidelines for the management of severe aortic stenosis. Eur Heart J. 2023;44(10):796-812. doi:10.1093/eurheartj/ehac803
17. Kappetein AP, Head SJ, Généreux P, et al; Valve Academic Research Consortium-2. Updated standardized endpoint definitions for transcatheter aortic valve implantation: the Valve Academic Research Consortium-2 consensus document. J Thorac Cardiovasc Surg. 2013;145(1):6-23. doi:10.1016/j.jtcvs.2012.09.002
18. VARC-3 WRITING COMMITTEE; Généreux P, Piazza N, et al. Valve Academic Research Consortium 3: updated endpoint definitions for aortic valve clinical research. Eur Heart J. 2021;42(19):1825-1857. doi:10.1093/eurheartj/ehaa799
19. Higgins JP, Jackson D, Barrett JK, Lu G, Ades AE, White IR. Consistency and inconsistency in network meta-analysis: concepts and models for multi-arm studies. Res Synth Methods. 2012;3(2):98-110. doi:10.1002/jrsm.1044
20. Abdelghani M, Mankerious N, Allali A, et al. Bioprosthetic valve performance after transcatheter aortic valve replacement with self-expanding versus balloon-expandable valves in large versus small aortic valve annuli: insights from the CHOICE trial and the CHOICE-Extend registry. JACC Cardiovasc Interv. 2018;11(24):2507-2518. doi:10.1016/j.jcin.2018.07.050
21. Ahmad D, Sá MP, Kliner D, et al Transcatheter aortic valve replacement in small aortic annuli: A propensity-matched comparison between intra-annular self-expanding valves and balloon-expandable valves. Cardiovasc Revasc Med. 2026;82:78-83. doi:10.1016/j.carrev.2025.05.009
22. Baudo M, Sicouri S, Yamashita Y, et al. Improved hemodynamics with self-expanding compared to balloon-expandable transcatheter aortic valve implantation in small annulus patients: a propensity-matched analysis. Am J Cardiol. 2024;221:9-18. doi:10.1016/j.amjcard.2024.03.042
23. Deeb GM, Chetcuti SJ, Yakubov SJ, et al J. Impact of annular size on outcomes after surgical or transcatheter aortic valve replacement. Ann Thorac Surg. 2018105(4):1129-1136. doi:10.1016/j.athoracsur.2017.08.059
24. Guimarães L, Voisine P, Mohammadi S, et al. Valve hemodynamics following transcatheter or surgical aortic valve replacement in patients with small aortic annulus. Am J Cardiol. 2020;125(6):956-963. doi:10.1016/j.amjcard.2019.12.020
25. Hase H, Yoshijima N, Yanagisawa R, et al; OCEAN-TAVI Investigators. Transcatheter aortic valve replacement with Evolut R versus Sapien 3 in Japanese patients with a small aortic annulus: the OCEAN-TAVI registry. Catheter Cardiovasc Interv. 2021;97(6):E875-E886. doi:10.1002/ccd.29259
26. Herrmann HC, Mehran R, Blackman DJ, et al; SMART Trial Investigators. Self-expanding or balloon-expandable TAVR in patients with a small aortic snnulus. N Engl J Med. 2024;390(21):1959-1971. doi:10.1056/NEJMoa2312573
27. Hioki H, Yamamoto M, Shirai S, et al; OCEAN-TAVI Investigators. Valve performance between latest-generation balloon-expandable and self-expandable transcatheter heart valves in a small aortic annulus. JACC Cardiovasc Interv. 2024;17(22):2612-2622. doi:10.1016/j.jcin.2024.08.049
28. Itach T, Loewenstein I, Zahler D, et al. Transcatheter aortic valve implantation in small and very small aortic valve annuli: a propensity-matched analysis between self-expanding versus balloon-expandable valves. Catheter Cardiovasc Interv. 2025;105(3):624-632. doi:10.1002/ccd.31374
29. Kalogeras K, Jabbour RJ, Pracon R, et al. Midterm outcomes in patients with aortic stenosis treated with contemporary balloon-expandable and self-expanding valves: does valve size have an impact on outcome? J Am Heart Assoc. 2023;12(11):e028038. doi:10.1161/JAHA.122.028038
30. Kornyeva A, Burri M, Lange R, Ruge H. Self-expanding vs. balloon-expandable transcatheter heart valves in small aortic annuli. Front Cardiovasc Med. 2023;10:1175246. doi:10.3389/fcvm.2023.1175246
31. Leone PP, Regazzoli D, Pagnesi M, et al. Implantation of contemporary transcatheter aortic valves in small aortic annuli: the international multicentre TAVI-SMALL 2 registry. EuroIntervention. 2023;19(3):256-266. doi:10.4244/EIJ-D-22-00843
32. Matsuhiro Y, Mizote I, Nakamura D, et al. Long-term bioprosthetic valve durability after transcatheter aortic valve replacement with supra-annular self-expanding versus intra-annular balloon-expandable valves in patients with a small aortic annulus. Catheter Cardiovasc Interv. 2025;105(5):990-997. doi:10.1002/ccd.31415
33. Mauri V, Kim WK, Abumayyaleh M, et al. Short-term outcome and hemodynamic performance of next-generation self-expanding versus balloon-expandable transcatheter aortic valves in patients with small aortic annulus: a multicenter propensity-matched comparison. Circ Cardiovasc Interv. 2017;10(10):e005013. doi:10.1161/CIRCINTERVENTIONS.117.005013
34. Modine T, Forrest JK, Van Mieghem NM, et al. Transcatheter or surgical aortic valve replacement in women with small annuli at low or intermediate surgical risk. Am J Cardiol. 2024;223:147-155. doi:10.1016/j.amjcard.2024.04.013
35. Okuno T, Tomii D, Lanz J, et al. 5-year outcomes with self-expanding vs balloon-expandable transcatheter aortic valve replacement in patients with small annuli. JACC Cardiovasc Interv. 2023;16(4):429-440. doi:10.1016/j.jcin.2022.11.032
36. Rodés-Cabau J, Pibarot P, Suri RM, et al. Impact of aortic annulus size on valve hemodynamics and clinical outcomes after transcatheter and surgical aortic valve replacement: insights from the PARTNER trial. Circ Cardiovasc Interv. 2014;7(5):701-711. doi:10.1161/CIRCINTERVENTIONS.114.001681
37. Sá MP, Ahmad D, Wang Y, et al. Supra-annular versus intra-annular self-expanding valves in small aortic annulus: a propensity score-matched study. Struct Heart. 2024;9(1):100334. doi:10.1016/j.shj.2024.100334
38. Scotti A, Sturla M, Costa G, et al. Evolut PRO and SAPIEN ULTRA performance in small aortic annuli: the OPERA-TAVI registry. JACC Cardiovasc Interv. 2024;17(5):681-692. doi:10.1016/j.jcin.2024.01.006
39. Yamamoto M, Ryuzaki T, Hioki H, et al, Ocean-Tavi Investigators. Intra- versus supra-annular self-expanding transcatheter heart valves in small aortic annuli. EuroIntervention. 2025;21(13):e749-e757. doi:10.4244/EIJ-D-24-00966
40. Ayyad M, Jabri A, Khalefa BB, et al. Efficacy and safety of TAVR versus SAVR in patients with small aortic annuli: a systematic review and meta-analysis. Int J Cardiol. 20245;411:132243. doi:10.1016/j.ijcard.2024.132243
41. Tabassum S, Burhan M, Shehada W, et al. Balloon-expandable valves versus self-expanding valves in patients with small aortic annulus undergoing transcatheter aortic valve replacement: a systematic review and meta-analysis. Cardiol Rev. 2025. doi:10.1097/CRD.0000000000001108
42. Baudo M, Sicouri S, Yamashita Y, et al. Balloon-versus self-expandable transcatheter aortic valve implantation in small aortic annuli: a meta-analysis of randomized and propensity studies. Cardiovasc Interv Ther. 2025;40(3):607-618. doi:10.1007/s12928-025-01105-w
43. Freitas-Ferraz AB, Tirado-Conte G, Dagenais F, et al. Aortic stenosis and small aortic annulus. Circulation. 2019;139(23):2685-2702. doi:10.1161/CIRCULATIONAHA.118.038408
44. Treibel TA, Badiani S, Lloyd G, Moon JC. Multimodality imaging markers of adverse myocardial remodeling in aortic stenosis. JACC Cardiovasc Imaging. 2019;12(8 Pt 1):1532-1548. doi:10.1016/j.jcmg.2019.02.034
45. Gavina C, Falcão-Pires I, Pinho P, et al. Relevance of residual left ventricular hypertrophy after surgery for isolated aortic stenosis. Eur J Cardiothorac Surg. 2016;49(3):952-959. doi:10.1093/ejcts/ezv240
46. Pibarot P, Weissman NJ, Stewart WJ, et al. Incidence and sequelae of prosthesis-patient mismatch in transcatheter versus surgical valve replacement in high-risk patients with severe aortic stenosis: a PARTNER trial cohort--a analysis. J Am Coll Cardiol. 2014;64(13):1323-1334. doi:10.1016/j.jacc.2014.06.1195
47. Sá MP, Jacquemyn X, Van den Eynde J, et al. Impact of prosthesis-patient mismatch after transcatheter aortic valve replacement: meta-analysis of Kaplan-Meier-derived individual patient data. JACC Cardiovasc Imaging. 2023;16(3):298-310. doi:10.1016/j.jcmg.2022.07.013
48. Voigtländer L, Kim WK, Mauri V, et al. Transcatheter aortic valve implantation in patients with a small aortic annulus: performance of supra-, intra- and infra-annular transcatheter heart valves. Clin Res Cardiol. 2021;110(12):1957-1966. doi:10.1007/s00392-021-01918-8
49. Levesque T, Eltchaninoff H, Chabannes R, et al. Impact of prosthesis-patient mismatch after transcatheter aortic valve replacement. Can J Cardiol. 2024;40(1):113-122. doi:10.1016/j.cjca.2023.09.012
50. Thyregod HG, Steinbrüchel DA, Ihlemann N, et al. No clinical effect of prosthesis-patient mismatch after transcatheter versus surgical aortic valve replacement in intermediate- and low-risk patients with severe aortic valve stenosis at mid-term follow-up: an analysis from the NOTION trial. Eur J Cardiothorac Surg. 2016;50(4):721-728. doi:10.1093/ejcts/ezw095
51. Schofer N, Deuschl F, Rübsamen N, et al. Prosthesis-patient mismatch after transcatheter aortic valve implantation: prevalence and prognostic impact with respect to baseline left ventricular function. EuroIntervention. 2019;14(16):1648-1655. doi:10.4244/EIJ-D-18-00827
52. Ternacle J, Theron A, Pibarot P. Prosthesis-patient mismatch after transcatheter aortic valve replacement: lower the guard or stay alert? JACC Cardiovasc Interv. 2024;17(22):2636-2638. doi:10.1016/j.jcin.2024.09.025
53. Guthoff H, Abdel-Wahab M, Kim WK, et al; IMPPACT TAVR Investigators. Impact of measured and predicted prosthesis-patient mismatch after transcatheter aortic valve replacement. JACC Cardiovasc Interv. 2024;17(22):2626-2635. doi:10.1016/j.jcin.2024.08.041
54. van den Dorpel MMP, Chatterjee S, Adrichem R, et al. Prognostic value of invasive versus echocardiography-derived aortic gradient in patients undergoing TAVI. EuroIntervention. 2025;21(8):e411-e425. doi:10.4244/EIJ-D-24-00341
55. Shan Y, Pellikka PA. Aortic stenosis in women. Heart. 2020;106(13):970-976. doi:10.1136/heartjnl-2019-315407
56. Tchetche D, Pibarot P, Bax JJ, et al. Transcatheter vs. surgical aortic valve replacement in women: the RHEIA trial. Eur Heart J. 2025;46(22):2079-2088. doi:10.1093/eurheartj/ehaf133