Chapter 2: Building Consensus: How the Recommendations Were Developed
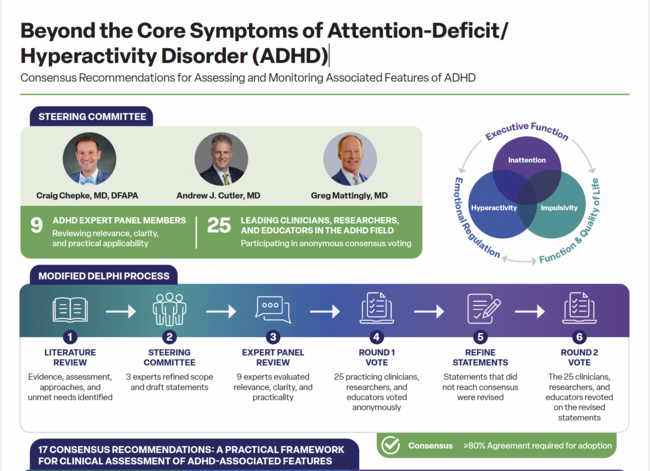
Expert panel members discuss the process behind the development of consensus recommendations for evaluating the associated features of attention-deficit/hyperactivity disorder (ADHD).
View the poster: Consensus Recommendations for Assessing and Monitoring Associated Features of Attention-Deficit/Hyperactivity Disorder in Clinical Practice.
Transcript
Greg Mattingly, MD: Craig, I know you pulled in some of the experts for that. So, what kind of experts did we bring into that 25-member panel to think about ADHD?
Craig Chepke, MD, DFAPA: That's exactly right, because their expertise can mean a lot of different things. There could be expertise in research, expertise in education, but also expertise clinically. We wanted to make sure that we weren't just looking at the theoretical aspects of this, but what about the boots on the ground? So, we got a broad spectrum of different types of expertise in that final consensus voting panel stage.
Mattingly: And we made sure we had diversity, right?
Chepke: Exactly.
Mattingly: So, we wanted younger clinicians, older clinicians. We wanted people who were academic thought leaders. We wanted people that came from minoritized backgrounds so that we really had a consensus reflecting...
Chepke: Hospital-based, private practice, all different types of spectrum to make sure that we're really encompassing the breadth of opinions on ADHD, and that we're really getting the best practices that we can.
Mattingly: I call it the ADHD ecosystem
Chepke: Right, love that.
Mattingly: We wanted to make sure we included that entire ADHD ecosystem. So, that could be nurse practitioners, that could be PhDs, that could be psychiatrists...
Chepke: Exactly.
Mattingly: ... child psychiatrists, and made sure we reflected the ecosystem of who tends to care and manage ADHD.
Andrew Cutler, MD: Well, I think, too, we wanted to make it clinically relevant, not just some academic esoteric statements, but really things that people in the clinics could use and be valuable.
Chepke: Right. For patients with ADHD to really benefit from this, it's got to be clinically actionable.
Mattingly: Yep. As we went through these statements, and we came up with a variety of statements that we thought could help move the needle, could help educate, could inform decision-making, practical guidelines about how to tackle these associated features, I think kind of the number we landed on is we had to have at least 80% consensus about any of these.
Chepke: Exactly.
Mattingly: Most of them the first time through had 80%. Most had unanimous consensus that, "Hey, this makes sense. We think it's actionable. It makes a difference. This makes sense." We had a couple that didn't meet the criteria.
Cutler: That's right.
Mattingly: So, how do we handle that, Andy? If something didn't meet 80%, what did we do?
Cutler: Well, what I really like was there was a great group process. We had several meetings where we got people together and got them to kind of workshop, edit, wordsmith. I found there was a lot of that that improved it and changed my mind on some of our statements.
Chepke: Well, I'm really glad that it wasn't always unanimous and didn't always meet 80% the first time around, because we don't want it to be just our opinions. That's why we had this multi-level process of bringing in so many people from that ecosystem. If it was unanimous every time of what we said, I would start to wonder, are we really pressure testing this? Compromise is sometimes looked at as bad, but we want to compromise and make sure that everyone is getting their accurate representations down so that we're really getting something that's going to stand the test of time.
Cutler: Yeah. I think actually, through the process, a lot of them got better, Greg.
Chepke: I agree. Totally.
Mattingly: They did get better.
Chepke: Everyone got better.
Mattingly: I know one of the things we worked on, and we modified our own kind of verbiage and language, because words matter.
Chepke: Sure do.
Mattingly: We very purposely made sure we were using non-stigmatizing language and empowering language, right?
Cutler: Yes, exactly.
Mattingly: So, we wanted to make sure that these were decisions that could empower, could make differences, and that it was non-stigmatizing in the way we were addressing it.
Cutler: That's right. You actually led that effort, I remember.
Mattingly: It was. I'll use one of my pet peeves. I don't like talking about drugs when we're talking about psychiatric medications.
Chepke: I could not agree more.
Mattingly: I don't give my patients drugs; I give my patients medications that have been shown to help with certain conditions or certain symptoms. So, removing any kind of those stigmatizing labels when we think about this. Let's talk about some of the results. So, when we think about the results, we had block 1, [which] was about how do we kind of look at the ADHD-related impairments? Going back to the diagnosis, you have to have impairments in 2 or more areas. So, we talked about how to measure impairment at school, at work, at home, socially, organizationally, emotionally. Where do we see impairment? Andy, you and I have been part of research studies where when we really target impairment in somebody's life, we do a better job of moving the needle.
Cutler: 100%.
Mattingly: So, these aren't symptoms that somebody else has; these are impairments that I have, and are those getting better?
Cutler: Well, Greg, this is a lifelong disorder, right? It's a neurodevelopmental disorder. So, when people come to see us, they've had symptoms for a long time. So, what's the why now? What brings them in now? It's very often...
Mattingly: You love the why now. I know.
Cutler: I do, but it's very often impairment or something like that. If we don't address that, the why now, whatever it is, it's going to be different for everybody. I don't feel like we're really getting all the way there.
Mattingly: Yeah, the why now is, "I almost lost my job."
Cutler: Exactly.
Mattingly: The why now is, "My wife says she can't take it much longer." The why now is, "God, I don't have any friends anymore. I've burned through so many relationships." The why now is, "I've started self-medicating and doing things I probably shouldn't be doing, and I can't get myself out of it."
Chepke: I find that the why now then leads us to backtrack to all the different times where they did have impairments, and then they just pivoted around and did something else, maybe took a job that was below what their IQ and potential would've been to avoid some of those things.
Cutler: That's such a good point. It's not always failure, it's underachievement, underperforming, not meeting your potential.
Chepke: That's right.
Mattingly: Or having to compensate by spending more time.
Cutler: Yes, yes.
Mattingly: Like, "I'm swimming as fast as I can, and there's just no time to take a breath, and I can't do it.”
Chepke: Compensating by overworking, giving up things like having friendships or relationships, that they sacrifice in order to get the job done that other people in the same position were able to do in much less time, and have more leisure time.
Cutler: Or the impact on someone else. The mom who has to spend several hours every night with their child organizing and preparing.
Mattingly: So, Craig, it was interesting. The valedictorian of my high school class, I later found out, had ADHD. So, she was number 1 in her high school class, she went to a college on scholarship, had a difficult time in college. I'm like, "How could she be having a hard time?" She said, "You don't know how hard I had to work in high school. I was already staying up till midnight studying when the rest of you guys were going to bed at 8:00. I got to college..."
Chepke: There's a limitation how far up the chain you can do that. You can compensate so long, but then you move up in a transition to high school to college, college to grad school, middle school to high school, wherever... it is different for each person. Those old techniques hit a brick wall headfirst, and you just can't do it. It's impossible.
Mattingly: Yep. So, we looked at the impairments. We then looked at assessment. So, how do we assess these different domains of impairment and symptoms going beyond just the typical ADHD RS checklist, or the ASRS? How do we assess it?
Cutler: Absolutely.
Mattingly: So, I think we're going to have some tips and tricks on how to assess it. We came up with some mnemonics to help people to remember how to assess it, but just how do we as a group think about how do we assess this? I think that's going to be one of the take-homes of this whole initiative.
Cutler: Oh, absolutely. I think most clinicians know how to assess the core 18 symptoms, but emotional dysregulation, executive dysfunction, it seems a little fuzzy or more nebulous. They're not as well-trained in that. So, we're hoping to really help people with that.
Chepke: Yeah, and the mnemonics are great to actually remember doing it. They could be in agreement that, yes, I should be looking for this, but if they can't remember it when the rubber hits the road, they're in the session with the patient, it's not going to matter. So, making those mnemonics, make it easy to remember, easy to actualize, that's going to actually result in the improvement in people living with ADHD.
Mattingly: So Craig, how many times have you sat in a lecture where you say, "God, this is really smart stuff," but when you leave it you either don't remember it or it doesn't make a difference in your practice?
Chepke: Yeah, exactly.
Mattingly: Okay. So, the next step we had was, let's take it from theory to clinical implementation. How do we make a difference in your practice when you go home and you take care of patients? So, that was block 3 of our levels of assessment. So, let's define the impairments, let's talk about how to assess them; let's talk about how to make a difference. Do you want to talk through some of the statements? We'll save this for the learners to learn a little bit later, but some fun statements we came up with, right?
Cutler: Sure.
Mattingly: So, what were some of the learnings? Craig, take us through a couple.
Chepke: Sure. The first statement was that we should use understandable, culturally appropriate, and non-stigmatizing language.
Cutler: Yes, exactly.
Chepke: Because it's so easy for us to slip into medical jargon as if we were talking to a colleague, when we need to recognize that people don't have the same... The reason why we're on this side of the room and they're on that side is we've had the education, we've had the training, and we're not doing our job as clinicians if we can't bring it to a level where we're both in alignment on what it means. That's incredibly important, because we got to give them a fair shake to be able to explain their experience by asking them questions in ways that they understand. We need to make sure that we're using patient-centered terms, emotional regulation, executive function, instead of emotional... Tell me about your emotional dysregulation, tell me about your executive dysfunction, tell me about what your executive function looks like. How do you regulate your emotions?
Mattingly: Throughout the guidances, Andy, we worked hard to pull the “dys-” out of it. Right?
Cutler: Yes, absolutely.
Mattingly: Get rid of the discord, get rid of the dysfunction, get rid of the dysregulation. Instead, we talked about emotional function. How do you function?
Chepke: The amazing thing is, it was so easy to do, and it means exactly the same thing by saying it in a way that is neutral, has a neutral connotation instead of talking about your dysfunction as if they're a bad person, they're misbehaving, they're doing something wrong, which is obviously not...
Cutler: Also, a lot of people don't know the terms. What does emotional regulation or executive function mean? So, we also have practical tips on how to give examples and what exactly do we mean by that.
Chepke: Right, because those buzzwords sometimes are well known, but then what do those buzzwords mean, and how do you actually utilize that in practice? That's much more challenging.
Mattingly: Okay, statement number 2 had unanimous consensus. I think it was our first unanimous consensus point, and we said, "We have to move beyond just ADHD symptoms, but we have to include functional impairment." That was an easy one because the diagnosis in DSM already tells us that, but...
Cutler: Yeah, but people don't always think that.
Mattingly: ... we forget it. Right, Andy?
Cutler: Yeah.
Mattingly: We do our checklist, and we forget to ask, "Okay, let's talk about your life."
Cutler: That's right. Also, those core 18 symptoms really were codified because they respond especially well to stimulants.
Mattingly: That's a great point.
Cutler: But we all know ADHD is much more than just that. So, thinking about all the whole package of ADHD means we have to really rethink, I think, our treatment paradigm.
Mattingly: Yeah. Item 3, got to move beyond just ADHD symptoms, but we have to include emotional regulation and executive function. How are you doing organizing things, running on time, remembering to pay your bills, all of those issues.
Cutler: Greg, they are in the DSM-5, they're called associated features. We also want to distinguish that from comorbidities. There certainly are comorbidities as well, and we'll talk about that too.
Chepke: Yeah, and I like how we really layered things and didn't make it over-complicated. First, we have to move beyond the core symptoms. Then, where do we need to move beyond the core symptoms and make it very stepwise and digestible?
Mattingly: Step 4 was that those issues cause functional impairment, and you need to remember that. Guidance number 5 is when impairments and emotional regulation are present, that we should always consider ADHD.
Cutler: Oh, I see.
Mattingly: So, one of the mistakes people make is, I come in with emotional regulation issues. "Oh, that's got to be depression."
Cutler: That's a mood disorder.
Mattingly: "Maybe you're bipolar spectrum."
Cutler: That's right, it's a mood disorder.
Mattingly: "Maybe your girlfriend has borderline personality disorder, sir," where really, it's untreated ADHD.
Cutler: Absolutely.
Mattingly: So, if you see emotional regulation issues on your hot screening ticket, it has to be ADHD.
Chepke: Yeah, a flag should go up, must screen for ADHD.
Cutler: Well, especially adults. They often present with the comorbidity as the tip...
Chepke: Very frequently, yes.
Cutler: ... of the iceberg. You’ve got to look under the water.
Mattingly: You're stealing my guidance number 6, Andy.
Cutler: There you go, I'm thinking ahead.
Mattingly: Okay, you are. So, mood and anxiety are common comorbid conditions. So, it can be emotional regulation due to ADHD itself, or it can be, "Listen, I'm overwhelmed. I'm despaired. I'm now stuck in my head. I've developed social avoidance and social anxiety. I've had so many blowups around people; I just don't go anywhere anymore." We've all had that patient, right?
Chepke: Mm-hmm, and then that usually craters inwards in their self-esteem of, "I mess up every relationship I have and friendship I have. There's something wrong with me."
Cutler: That's right. The neurobiology also helps us understand this, because the most common finding, the most consistent neuroimaging finding, is hypofrontality. The frontal lobes, what's their job? Well, it's top-down regulation of the emotions, and it's executive function. One of the problems with ADHD is the part of the brain that involves self-observation, insight, and judgment is faulty. So, they of course have trouble with self-regulating; shifting is a big problem. Shifting, attention shifting, tasks, they get stuck.
Mattingly: Yeah. Thoughts become emotions, become actions.
Cutler: Love that.
Mattingly: If you can't modulate that cascade, you can see where it gets off track.
Cutler: Love it
Mattingly: Okay, Andy, this one's yours.
Cutler: Okay.
Mattingly: I'm going to give you credit. You came up with the 5Rs, right?
Cutler: Yes, I did.
Mattingly: Walk us through the 5Rs that we want to screen for. Where are we going to look for impairment in people's lives?
Cutler: Well, you know where this comes from, Greg? You and I do a lot of research, and we use rating scales. I realize a lot of clinicians are intimidated by rating scales, they don't feel like they need training, whatever. So, I was trying to think of some way of really systematically evaluating, but especially almost creating a rating scale that's specific to that patient. I thought, "Well, what are the areas?" So, I came up originally with 4Rs, and we added a fifth. Those are, “What is the patient's roles? What are their responsibilities? What are their important relationships? What do they like to do for recreation, for fun?” We forget sometimes if somebody's spending all this time compensating, they're not having fun.
Mattingly: That was my friend in high school.
Cutler: Yeah, exactly. Right? Then what we added, which I think is so important, is resilience. What do you do for resilience to be able to... Look, we can't go through life without having stress, without having loss and change. How do we cope with that? So, I'm very proud of that. Of course, if you do that with the patient, what you do is you write it in the chart, and then you just ask about those specific things. Guess what? Boom, you've created a rating scale that's personalized, individualized to that patient.
Mattingly: Yep. So, "Ma'am, let's talk about your roles. What things do you have to do in life? What are your responsibilities? What are your important relationships? What do you like to do for fun and recreation? How do you do under stress?"
"I'm okay on a good day, but I fall apart on a bad day." "How is your resilience?" I love it, the 5Rs. Let's talk about our next statement. Craig, I'll let you handle this one.
Chepke: Well, this one, I've got to give full credit to Andy too. It's the why now. That when we do the assessment, we need to explore what brought you to treatment. Generally, people don't ask for help with mental health conditions until there's some sort of, sometimes they call it a near miss, that, "I almost just lost a relationship," or a job, or, "Something almost just blew up in my face," and they get scared, and that's when they want to come to treatment. So, why now? Because so rarely is the case that someone comes in, and, "Oh, this just started 2 weeks ago," and that's accurate. It's that something happened now, but they could have come in 2 weeks ago, 2 months ago, 2 years ago, and gotten help at that point. So, why now? That's really critical to figure out the lens of how we need to view their overall course.
Cutler: The why now is different for everybody. What's interesting, Greg, we've talked about this before. A lot of times, people come in when they're in crisis, and something bad's happening, but with adults, sometimes I've noticed they come in when something good is happening in their life, but they can't manage it. For instance, you get a promotion at work. Now you have more cognitive load, "I've got to manage more things." I had a woman who came in when she had another child, now she had to manage... I mean, these are good things in people's... "I want to go back and finish my degree," for instance. So, sometimes those things can precipitate. It's like we said before, the valedictorian, now she goes to college, she has more to manage, she has to function more independently, and the wheels fall off at that point.
Mattingly: Okay. Statement number 9. In some ways, it's self-evident, but in some ways, we miss it, that life is a journey. ADHD isn't just kids, it's not just adolescents, it's not just college. So, when we talk about the assessment of emotional regulation and function, we should talk about where they are developmentally. I want my 12-year-old to be able to function like a 12-year-old, not still be functioning like an 8-year-old.
Cutler: Exactly.
Mattingly: I want my 21-year-old to be able to manage their own money, not be having to have their mom manage their money and pay their bills. So, are you functioning at your level developmentally when you think about it? So, that's statement number 9. Statement number 10. This is another mnemonic. I know this is another one. We all kind of had fun with this one. We talked about planning, organization, time management, and self-monitoring. Am I able to pick up that, "Hey, I've talked too much"?
"Hey, I'm starting to lose it. Hey, I need to get moving with what I should be doing." So, we call this one the POTS, right? So, we want to remember to do our POTS, planning, organization, time management, self-monitoring.
Cutler: This is a mnemonic for executive function specifically. We were trying to give people a way to remember what is executive, what are the aspects of executive function? There's many.
Chepke: Yeah, and there's many aspects, but I think narrowing it to these that are easily memorable will make it more likely clinicians will assess for them regularly. That's really the key is; if there's not regular routine assessment, then we're doing an injustice to people with ADHD.
Mattingly: I would bet of all of these, the one that we tend to forget as a clinician is the self-monitoring.
Cutler: Yes. You can call that insight, you can call that self-organization, but that self-monitoring and awareness.
Chepke: How can they read the room?
Mattingly: Correct.
Cutler: It's reading the room.
Mattingly: Okay. Statement number 11. Statement number 11, then, is talking about emotional regulation. So, we had POTS. If you have POTS, you’ve got to have...
Cutler: PANS.
Mattingly: Got to have PANS. So, what are the emotional regulation symptoms we want people to clue into, Craig?
Chepke: Well, there's different domains that you have to assess the positive emotional regulation and the negative emotional regulation, because it's easily understandable about how can you manage your negative emotions? But some people with ADHD, they can't regulate their positive emotions. They're too much, they're extra sometimes, as I've heard. You have to manage both domains. We put POTS and PANS as memorable acronyms and link them together, because executive function and emotional regulation, I think we all agreed, were the 2 most important associated features of ADHD that have historically gone unrecognized after the core symptoms.
Cutler: I think we also agreed that they contribute a lot to the impairment and to the why now very well.
Mattingly: Yeah. I love PANS as an acronym, because it's positive and negative.
Cutler: Yes.
Mattingly: It's easy to always hone in on the negative...
Cutler: I agree.
Cutler: So well said.
Mattingly: So, we can be both sides of that emotional equation that can be dysregulated.
Cutler: Well, when we talk about regulation is regulating across the spectrum. It's not just like you said, blowing up…
Chepke: Too much isn't good, and too little is not good.
Mattingly: Okay. So, emotional regulation. Craig, I think this was yours.
Chepke: Yes.
Mattingly: Emotional regulation can sometimes be really rough for our patients. That's our next mnemonic, right? So, RUF stands for...?
Chepke: Rejection, understimulation, and frustration.
Cutler: Right, I love that. And we used the U, understimulation. I want to clarify that also includes boredom.
Chepke: Exactly.
Cutler: I like to say, sometimes with ADHD, boredom is your mortal enemy, and there's almost frantic attempts to avoid boredom.
Mattingly: We also know now from neurologic studies that the ADHD brain does great when they find an activity stimulating enough, interesting enough. That's what we've always seen, but they can't shift to a nonstimulating, understimulating behavior.
Cutler: Well, part of the problem is that the name itself is kind of wrong. It's not attention. How often have we had a mom come in and say, "My son doesn't have... He can pay attention; he can play video games for hours." So, it's really all or none. It's attention, regulation, modulation, and that holds true for everything we're talking about.
Mattingly: What's our next one, Andy?
Cutler: Well, the impairments are on a continuum. They're not always things completely exploding and blowing up. So, you don't want to just look for high impairment. I like what we said before about underachieving or not reaching potential. Yeah, okay, this kid's getting Bs. He's doing fine, what's the problem? What if this is an A+ potential student? So, we want to rate impairment on a continuum, if you will, and be clued into... I think about your valedictorian. I had a professor once who said, "IQ points can compensate for a lot." So, the smarter kid may be fine in high school, but then when you get onto where you really have to manage things, that's what...
Chepke: Yeah, like Greg's friend, she could brute force IQ her way through high school, but you can't do that at college level.
Mattingly: I also think this next one gets into... Andy, it's easy to overlook the people that don't have high impairment.
Cutler: Yes.
Mattingly: Russ Barkley used to talk about the kid who's sitting in the back of the room just checked out.
Cutler: That's right.
Chepke: Flying under the radar.
Cutler: That's right.
Mattingly: Yeah, no, he's not running around the room, he's not blurting things out.
Cutler: No, he's not.
Mattingly: He's not blowing up and throwing things. He's just checked out and underperforming. He's not getting to where he should be in life.
Cutler: Absolutely. Absolutely.
Mattingly: Next statement, Craig, take us through the next one.
Chepke: Well, rating scales are great, but rating scales for clinicians may be impractical. They may not know how to utilize them and score them. Some rating scales may have certain rights limitations, but they can really help structure the clinical assessment and identify the domains that we need to have further questioning and monitoring for. So, we may not be able to use rating scales always, but we need to be able to make sure that we can use them in the right situations at the right times.
Cutler: Rating scale is just systematically assessing...
Chepke: Exactly.
Cutler: ... the same thing. That's why I liked that I came up with the 5Rs to just have certain things that you're monitoring at each visit.
Mattingly: Roles, relationships. Yeah, resilience. I love that, Andy, because it is what you get down to in the end.
Cutler: Sure, sure. Are you a homemaker? Are you a student? That's kind of the role thing. Responsibility...
Chepke: Well, and usually, there's multiple roles. You're a homemaker, and you're a mom, and you a volunteer, and you're a sister, and...
Cutler: Your responsibilities. You're a caretaker for an elderly parent.
Mattingly: Okay. The next guidance comes into we want to make this actionable. So, how do we monitor if people are getting better or not, Craig? When we look at these associated features, when we look at these impairments, how do we monitor and check, "Hey, are we getting better? Did we really get where we want to be, or are we still kind of struggling?" So, walk us through the next guidance.
Chepke: Yeah. We need to make sure that we're assessing those things and not just saying, "Oh, are you better?" Because patients, in my experience, will index on, "I can focus and concentrate great," or "It's much better." They're not thinking about it, but because those often aren't the big things that cause the biggest impairment, then we need to make sure we're assessing and using specific questions. We can repeat them consistently. Like you said with the 5Rs, mark it down in the chart and keep coming back to it; make sure that we're being comprehensive and longitudinal.
Cutler: Specific things to that patient, not just, "Do you have trouble paying attention?" "But remember, you told me you're having trouble when you're sitting in the classroom or in church? How's that going?" That's more specific and patient-relevant.
Mattingly: Yeah. Our next guidance, number 16, our second-to-last, our penultimate guidance. The penultimate guidance comes down to something you've mentioned, Andy, and we've all talked about, and that is that underachievement. So, on the surface, it looks like things are okay. I remember talking to a patient. The patient had a job, was working in retail, and the person said, "Dr Mattingly, I graduated with a 3.8 GPA, but the best job I seem to hold these days is able to hold in retail." Nothing wrong with retail, but he knew he was underachieving. On the surface, that looked okay. We also get into my high school friend having to use excessive amounts of time and emotional energy to compensate. So, the next guidance is don't overlook the person who's underachieving or the person who's frantically trying to keep up, to keep their head above the water.
Cutler: I'll never forget, I had a patient who was a salesman. He was a very good salesman, and they kept trying to promote him and he kept resisting because he didn't want to be in management where he knew the wheels would fall off and he couldn't manage it.
Mattingly: Andy, I'm taking care of a patient right now who's a doctor. He was on the no-bed list at the hospital because he wasn't getting his charts done.
Cutler: Yes, exactly.
Mattingly: Great physician, frantically trying to keep up, then starts procrastinating, gets overwhelmed, builds anxiety about it. So, those things happen. On the surface, he looks like he's great, but underneath that surface, he's scrambling pretty quick.
Cutler: Well, that's a great example of executive function impairment. That's not one of the obvious core symptoms of ADHD, but that's executive function
 Craig Chepke, MD, DFAPA
Dr Craig Chepke is a board-certified psychiatrist in clinical practice as the medical director of Excel Psychiatric Associates in Huntersville, North Carolina. He serves as an adjunct associate professor of psychiatry for the Atrium Health Psychiatry Residency Program and is the chief medical officer of Psych Congress. As part of an interdisciplinary treatment team in his practice, he employs a person-centered care model to tailor treatments to each individual's needs, integrating traditional pharmacotherapy with psychotherapeutic and physical health and wellness interventions. His clinical and academic interests include serious mental illness, movement disorders, ADHD, and sleep medicine. Dr Chepke has been recognized as a distinguished fellow of the American Psychiatric Association and is a recipient of the National Alliance on Mental Illness Exemplary Psychiatrist Award.
 Greg Mattingly, MD
Dr Greg Mattingly is a physician and principal investigator in clinical trials for Midwest Research Group. He is also a founding partner of St Charles Psychiatric Associates and an associate clinical professor at Washington University. A St Louis native, he earned his medical degree and received a Fulbright scholarship while attending Washington University. Dr Mattingly is board certified in adult and adolescent psychiatry, and he is a diplomate of the National Board of Medical Examiners. He has been a principal investigator in over 400 clinical trials focusing on ADHD, anxiety disorders, major depression, bipolar disorder, and schizophrenia. Having served on numerous national and international advisory panels, he has received recognition for clinical leadership and neuroscience research. Dr Mattingly is also the president of the American Professional Society of ADHD and Related Disorders and a member of the Scientific Advisory Board for the World Federation of ADHD.
 Andrew Cutler, MD
Dr Andrew J. Cutler is a clinical associate professor of psychiatry at SUNY Upstate Medical University in New York, and he serves as the chief medical officer of the Neuroscience Education Institute. He received his MD from the University of Virginia School of Medicine, where he was also elected to the Alpha Omega Alpha honor medical society and received the Merck Award for outstanding medical scholarship. He completed his medical internship, internal medicine residency, and psychiatry residency at the University of Virginia Medical Center, where he served as chief resident of psychiatric medicine and did research on dopamine receptor pharmacology. Dr Cutler then served as the first assistant professor and director of psychiatric medicine at the University of Chicago. He is board-certified in both internal medicine and psychiatry. Dr Cutler has also been the principal investigator on over 400 psychiatric and medical clinical trials.
This program was independently developed with funding from Otsuka Pharmaceuticals.